
P’s objections to early evening curfew are “compelling” evidence of deprivation of liberty after AGNI

By Celia Kitzinger, 12th October 2026

In recent months, we’ve observed dozens of hearings at which judges have ruled as to whether or not the residence and care arrangements of a protected party amount to a deprivation of liberty. I’ve observed some of these hearings myself; others have been reported by fellow observers.[1]  Taken together, they offer an emerging picture of how the Supreme Court’s decision in A Reference by the Attorney General for Northern Ireland [2026] UKSC 16 (AGNI) is changing the way deprivation of liberty is understood and determined in practice.

As expected, many people previously considered to be “deprived of their liberty” under the Cheshire West interpretation of Article 5 of the European Convention on Human Rights are now being found not to be deprived of their liberty under the new AGNI approach. The consequence of this is that the “deprivation of liberty safeguards” [DOLS] – safeguards like independent assessments, a Relevant Person’s Representative (RPR), the right to review and challenge – are removed from them.  This is a significant and controversial legal development.  National charities have warned that it strips essential human rights protections from potentially hundreds of thousands of disabled people and is “the biggest rollback of disability rights in a generation”. 

Against that background, how courts determine whether someone is deprived of their liberty after AGNI is a matter of legitimate public interest. The question is not simply how the new legal test is to be understood in the abstract. It is how judges apply it to the circumstances of individual people, what weight they give to the different factors, and how they explain decisions that may determine whether a person continues to receive important legal protections.

The answer to these questions is often not transparent for public observers watching these hearings. In many cases, all the parties agree[2] that the AGNI interpretation means there is no deprivation of liberty and the matter is not explored in any detail. These cases are in court for other reasons: e.g., contact arrangements, breached orders, P’s capacity and best interests in relation to decisions in other domains. Deprivation of liberty can appear almost in passing, as an administrative matter to be signed off along the way. The reasoning may be brief, with little explanation of how the legal test applies to the particular facts or why the parties’ shared position has been accepted.

The result is a troubling gap in public understanding. Observers may watch decisions being made that remove deprivation of liberty safeguards without learning much about P’s living arrangements, the restrictions to which P is subject, or the features of their circumstances that now place them outside the legal definition of deprivation of liberty. We can see the outcome, but not necessarily how the court got there.

That gap would matter less if the application of AGNI appeared straightforward and consistent across cases. But my experience of contested hearings has left me with questions. I have observed 18 cases in which the parties disagreed about whether P was deprived of their liberty after AGNI. None has resulted in a published judgment. In these hearings, I have sometimes been surprised by the arguments advanced by the parties, by the way judges have engaged with those arguments, and by the conclusions they have reached.

This causes me some concern about the basis upon which deprivation of liberty decisions are made in non-contested cases. The fact that everyone agrees a person is not deprived of their liberty doesn’t in and of itself make that the correct decision. It’s inevitable that AGNI’s  “multi-factorial” test leads to a wider range of factors being considered in arriving at a decision as to whether or not P’s circumstances are such as to constitute a deprivation of liberty.  It’s often said that decisions are now more “nuanced”, so  maybe what looks to me like inconsistency across cases is simply exquisite judicial sensitivity to the unique particulars of each case. And the implications of AGNI are still being  worked out in practice and have evolved over the four-month period since AGNI, as successive judgments have been published.[3]  Nonetheless, it’s fair to say that judicial decisions about whether or not P is deprived of liberty are turning out to be problematic for a court that is said to aspire to transparency with regard to the way in which judges are arriving at their decisions. (Check out the Postscript to this blog post for the way in which listing practices add to the transparency problem.)

Where a decision determines whether a person retains important safeguards, it matters that we can understand the basis on which it is made. That is not an argument for treating every agreed position as suspect, or for expecting a lengthy judgment in every case. It is an argument for taking seriously the judicial responsibility to explain decisions sufficiently for them to be understood, particularly where the legal framework is new, its practical implications are still emerging, and the consequences for the person concerned are substantial.

It is against that background that I welcomed the opportunity to observe this hearing (COP 13851951) before District Judge Callaghan sitting in Chelmsford County Court on Friday 2nd October 2026, at which there was a dispute between the parties as to whether or not P’s residence and care arrangements constitute a deprivation of liberty. The different positions advanced by the parties were presented in oral submissions, and decided in an oral (ex tempore) judgment[4] over a hearing that lasted most of the day.

The hearing therefore offered something that is missing from many of the cases I have observed: an opportunity to hear the arguments on both sides, to see how the judge approached them, and to understand the reasons for the decision. I doubt the judgment will be published, so this blog post is likely to be the only public record of the court’s decision and of the process by which it was reached. Regrettably, this is the case for most court decisions about deprivation of liberty.

Background to this case

The young man at the centre of this case (P) is in his early 20s and has “severe autism and a learning disability”. He also has gastro eosinophilic duodenitis which requires him to follow a restricted diet. His mother says he has a diagnosis of PICA. but this is contested or “downplayed” by the ICB and the care providers  -who acknowledge that P likes to put non-edible objects in his mouth but state that he rarely eats them.

He lived with his mother until he was 18 and moved to his current placement in 2021. He receives 24-hour care, funded through NHS Continuing Healthcare (CHC).  He lives in supported living accommodation, with care-agency staff supporting him on a 1:1 basis at home (though this reduces depending on the number of residents at any one time) and 2:1 when he is out in the community.  He has a Positive Behaviour Support (PBS) plan which permits staff to use physical restraint (a one arm release variation technique) as a last resort.

His parents are separated but he maintains a relationship with both of them and with his extended family. Each parent visits him weekly and also has contact by FaceTime. All parties except P’s mother consider it to be in his best interests to remain in his current placement with his existing care package. In any event, it has been determined during these proceedings that there is no available alternative placement on offer.

The dispute between P’s mother and the care providers

The current proceedings began with an application by the  ICB on 5th November 2024 (pre-AGNI) seeking authorisation of P’s deprivation of liberty at H House.[5] The proceedings have also involved a protracted dispute about P’s mother’s contact with him and with the staff responsible for his care.

At a hearing on 30th June 2025, HHJ Capon granted an interim injunction, endorsed with a penal notice, against P’s mother.  The ICB had applied for the injunction on an urgent basis, arguing that her behaviour threatened the stability of the placement, which was said to be “on the brink of giving formal notice”. The evidence relied upon concerned her conduct, which she disputes. A few months later, at a hearing on 31st October 2025, the injunction was replaced by an agreed “Schedule of Agreement” (also described as a “Contract of Expectations”). This largely reproduces the terms of the injunction.

The Schedule, which remained in place at the time of the hearing I observed, regulates P’s mother’s contact both with her son and with the staff caring for him. The ICB says it was necessary because of incidents in which she was allegedly rude to staff, removed items belonging to P, and visited without appointments or at inappropriate times, sometimes arriving early or late. The ICB also says – more recently, I think – that she sometimes fails to attend scheduled Sunday visits, upsetting P who is disappointed not to receive the expected visit. There have also been disagreements about P’s medical care. Under the Schedule, P’s mother has agreed not to initiate conversations or raise questions about his medical care.

From the ICB’s and care provider’s perspective, the Schedule is working well. P’s mother takes a very different view. She considers the restrictions unnecessary and disputes the account of her behaviour that led to them being imposed. She says that some of the difficulties arose because she was legitimately questioning the care her son was receiving, or because the placement had failed to provide her with information she needed, including information at handover about his medication and what he had eaten.

She feels that she has been “maligned” and “victimised” by the care provider after raising concerns about the quality of his care. As she put it to the court: “because I raised concerns, it led to an injunction being created against me to deflect those concerns. This is a pattern of behaviour from [the care provider]. When I raise concerns about any matters, I am met with contact restrictions”[6].

These are sharply contrasting accounts of the same relationship. The ICB and care provider consider the restrictions necessary to sustain the placement and manage contact; P’s mother considers them unjustified and connected to her attempts to raise concerns about her son’s care. The history matters because the dispute about P’s residence and care arrangements cannot readily be separated from the wider disagreement about the quality of his care, his mother’s role in his life, and the extent to which her concerns are being heard.

Why the case came back to court

After the last hearing, on 31st October 2025, everyone except P’s mother agreed that proceedings should now conclude. However, the parties could not agree on the terms of a final order.

P’s mother wanted to be released from the Schedule of Agreement.  She also wanted the search for alternative placements to remain open, since she had continuing concerns about the care P was receiving at H House. She also believes that he is deprived of his liberty there.

The final hearing was initially listed for 4th March 2026, but the proceedings did not conclude then. Further evidence was directed, and the final hearing eventually took place on 2nd October 2026, seven months later.[7] It was listed as a contested, full-day hearing.

During the hearing I observed, P’s mother agreed to remain bound by the Schedule of Agreement, as it became apparent that the ICB would otherwise apply for an injunction.  She continued to argue that these proceedings should not conclude.  However, there were still no available alternative placements for P, and the judge considered that her other concerns (about his healthcare and visiting arrangements) could be addressed outside the proceedings.

The hearing therefore focused primarily on whether P’s current residence and care arrangements amount to a deprivation of liberty under the law as clarified by AGNI. This is the issue I focus on in this blog post. But the wider context is important: the court was considering P’s liberty against a background of disagreement about his care, restrictions on his mother’s contact and involvement, and a prolonged dispute that had not resolved to her satisfaction.

The hearing

The applicant was NHS Mid and South Essex ICB, which is responsible for arranging P’s care, represented by Susanna Rickard of Serjeants’ Inn Chambers as counsel, and Beth Farrow of Mills & Reeve as the instructing solicitor.

There were three respondents: 

  • P (by his litigation friend the Official Solicitor), represented by Felicity Williams of Garden Court Chambers as counsel and Cerise White of Miles and Partners as the instructing solicitor.  (Interestingly, Cerise White also acted for the protected party in the case of Oxfordshire County Council v P and G [2026] EWCOP 33 (T2), one of the (now) five published judgments in this area.)
  • P’s mother (as a litigant in person on this occasion – she’d been represented by Anna Bicarregui of 39 Essex Chambers at the previous hearing); at this hearing the mother was supported by a McKenzie Friend.
  • P’s father (also as a litigant in person, as he had been at the previous hearing).

At the outset, the judge made clear that “this case has been before the court long enough and there needs to be resolution”.  Two versions of the draft order had been filed for her consideration. As she observed, “the only real difference is the deprivation of liberty point”.

Those opening remarks framed the task before the court: to bring protracted proceedings to a conclusion, primarily by resolving the question of whether P’s current arrangements amount to a deprivation of liberty.

Submissions concerning P’s deprivation of liberty

I’ll report on each party’s position in turn, in the order in which they made submissions.

The ICB’s position: P is not deprived of his liberty

Counsel for the applicant ICB pointed out that “the AGNI case has obviously changed the territory significantly”. The question of whether P’s residence and care arrangements now amount to a deprivation of liberty is one that the ICB “says candidly that it’s a lawyer’s question, and that must be correct”. 

The ICB Position Statement sets out (counsel said) “that it’s possible to fudge this and to make an order that used to be commonplace before Cheshire West to the effect that ‘to the extent that he’s deprived of his liberty, it’s authorised’. But (she said) that’s not appropriate here, “because there’s sufficient evidence for the matter to be determined. It is the submission for the ICB, having examined P’s care and his reaction to it, that this does not fall into a ‘deprivation of liberty’ and might be quite far away from it”.

I do not have the ICB’s Position Statement, so the account that follows is based on the oral submissions only. I have not been able to verify every passage against the written document.

Counsel summarised the ‘objective’ and ‘subjective’ elements of the multi-factorial’ assessment required by AGNI. The objective element concerns confinement to a particular restricted space for a material period of time (the paradigm case being the prison cell) – and relevant factors include the possibility of leaving, the degree of supervision and control over their movements, the extent of their social isolation, and restriction of social contacts. 

Counsel argued that AGNI “elaborated beyond domestic case law on the way in which an individual’s response to their living situation is actually part of the multi-factorial assessment of whether the objective element of confinement is met … Valid consent is an autonomous concept within Article 5, not to be equated with capacity”.  Counsel referred to §3 of her Position Statement (which I don’t have) where she quoted from AGNI – and I think it was this extract she was quoting:

“…. an individual without legal capacity under domestic law, but who is conscious of their environment and has a basic understanding of their living circumstances so that they can express their view about their situation, who manifests their acceptance of the situation they are in, should have their opinion respected when an assessment is made of whether they are deprived of liberty under article 5.” (§53(2) AGNI). 

She submitted that this was relevant to P in this case because “he is ‘manifesting his acceptance of the situation he is in’  – to use the  Supreme Court’s words.  In fact, it is more than acceptance. He enjoys living where he is and he is thriving and happy there.” She added that the word his father had used was ‘flourishing’”.

Counsel described P as clearly aware of his living arrangements: “He’s an active and animated young man. He’s engaged with his carers and recognises them. He loves his home.” The significance of P’s positive response, she argued, is that “ultimately AGNI makes clear that the court has to ask whether P’s living arrangements amount to a detention that’s against his wishes, or does it constitute a supportive home environment”. 

Counsel accepted that P’s Personal Behaviour Support Plan provides for restraint as a last-resort intervention, but said it was seldom used.  “Overwhelmingly, P is happy in his own environment”. 

In §6 of counsel’s Position Statement, counsel had apparently set out  the kinds of behaviours that might indicate objection to a person’s living arrangements. I don’t have that document and I don’t know the source of the list she gave. I didn’t succeed in capturing all of the objections she cited but they included, conflict, arguments, attempts to leave, and physical restraint.  “In my submission,” she said, “that description is far from fitting P”.

She argued that P “can’t be described as merely acquiescing in his care. He is happy” – and that “the so-called restrictions that form part of P’s care are imposed solely for the purpose of enhancing his quality of life: (not for punishment or coercion, but for his protection (see §130 AGNI). 

Counsel concluded with a strongly positive account of P’s life at the placement.  “It is the opposite end of the spectrum to a prison cell. P is happy. P shares his home with another service user and they have a positive relationship – it is more akin to friendship than housemate. He has a very varied program of activities. He has rewarding family relationships. He goes out into the community. He is not isolated. There is no element of coercion. His care is facilitative of his well-being and happiness and quality of life, and his experience is positive.” 

She also relied on P’s father’s description of  P as “happy and content”. His father considers that P receives “outstanding care” and has “a very special bond with both staff and his housemate”.

Counsel’s conclusion was that, in these circumstances, “the court is very far from being able to find that the objective element of confinement is met in those circumstances”.

The Official Solicitor’s Position: P is deprived of his liberty

The Official Solicitor advanced a different position to that of the ICB: “Contrary to the position of Ms Rickard, the position of the Official Solicitor is that we are not at one extreme.  A more nuanced approach is needed.”

Counsel emphasised that  P is subject to several care plans: the NHS CHC statutory care plan, the placement care plan and the Personal Behaviour Support plan, which provides for  restraint as a last resort.  In addition, the Schedule governs how contact between P and his mother operates. The Official Solicitor submitted that these arrangements need to be considered together, rather than the placement being characterised simply as a supportive home environment.

Counsel read out some paragraphs from the Department of Health and Social Care’s {DHSC] preliminary Guidance published on 15th June 2026, which addresses the relevance of objection to the assessment of deprivation of liberty: “It should be noted that the issue of whether a person is objecting to the confinement is relevant to the question of objective deprivation of liberty. Where a person is objecting, then it follows that valid consent is unlikely to be present. If there is an absence of objection when the person is capable of objecting, then it is more likely that the person is not being confined.”

The guidance goes on to say that objection may take different forms, including attempts to leave, refusal of care or treatment, physical resistance to care, restraint or one-to-one support to manage behaviour, and the use of covert or sedating medication in circumstances where a person objects.

Counsel then identified what she considered to be the relevant indicators of confinement and control in P’s own circumstances. These included locked entry and exit doors; one-to-one support during the day and hourly observations at night; supervision during personal care; and the arrangements governing visits and contact.

She submitted that P is not free to leave.  He can only access the community with carers, and when he does, carers are on hand at all times.  One example was given: “if he goes the swimming pool, he is not permitted to go down the flumes because of the risk to him”.  More generally, “he isn’t able to come and go at will – that depends on the availability of carers”. 

Counsel also drew attention to the difficulty of ascertaining P’s preferences. He “can’t express his preferences easily”, she said, referring to a recent visit by his solicitor at which he had not been able to engage with her. She quoted the Supreme Court’s warning in AGNI that the views of people with impaired understanding may not always be easy to ascertain: “[I]t may sometimes be difficult to ascertain the true feelings or preferences of vulnerable individuals who do not have mental capacity to decide on their living arrangements. The approach should be practical and realistic. Where there is serious doubt, no inference of valid consent should be drawn” (§53(v), AGNI, my emphasis).

The Official Solicitor’s argument therefore placed emphasis not only on the restrictions in P’s daily life, but also on the difficulty of establishing his wishes and preferences with confidence. Against the ICB’s account of a young man who is happy and flourishing, the Official Solicitor invited the court to consider the extent of P’s dependence on others, the limits on his freedom to come and go, and the uncertainty surrounding his ability to communicate his views.

The central difference between the two submissions was not whether P enjoyed important aspects of his life at the placement. It was what that evidence, alongside the restrictions on his movements and the difficulty of ascertaining his wishes, meant for the legal assessment of deprivation of liberty.

P’s mother’s position: P is deprived of his liberty

At the previous hearing (when she was represented)[8], P’s mother had raised concerns about whether the care and support that P is receiving is in his best interests. She thought he was not being offered activities that would motivate him to leave the placement. She expressed concern that, due to staff shortages, P is usually unable to leave the placement after 8pm. She said his bedtime routine can start as early as 5pm and that he’s often had a bath and dinner by 6.30pm, which leaves him unstimulated.  This theme continued in today’s hearing.

For P’s mother, it was important that the judge consider an incident recorded in the hearing bundle, which she described as having occurred “when he wasn’t allowed to go out that night”.

It took some time to locate the relevant entry. The mother described an occasion when P asked a member of staff whether he could go out sometime after 6.30pm. The worker said no because the shops were shut. P then became “very, very distressed” and bit the service user with whom he lived.

The mother was concerned about the consequences of restricting P’s activities, both for him and for the other people living at the placement:  “My concern with this in general is that he’s a risk to the other service users that he lives with, because his behaviour escalates when he’s subject to restrictions”.

She contrasted this with the arrangements when she cared for P at home: “When I looked after him at home, he led and I followed. That isn’t the case at H Home”. On the night in question, an on-call worker had been available to take P out for a drive, although not out into the community for an activity. Without that intervention, she said, it was impossible to know how his behaviour might have escalated. In her view, restrictions on going out increased the risk of P harming other residents and being restrained.

She also drew attention to the physical environment. Although the residence was “homely”, and in a pleasant area, she described the communal space as very small, given that P and his co-resident are each supported by their own staff.

The relevant entry was eventually located[9] and the judge read it aloud. It was a staff record dated 4th July 2026 and it was broadly consistent with the mother’s account: when told he could not leave the home, P had bitten his co-resident and “head-locked” a member of staff (according to the records). 

The mother said that this was not an isolated example. She believed other entries showed that staff themselves were recording P’s distress when he was prevented from going out.placed the incident in the context of a longer-running disagreement about P’s evening activities. She told the court that, when proceedings began in 2023, she had asked for evening activities to be provided. Various promises had been made, she said, and she had agreed to drop her application to become P’s deputy. In her view, those promises had not been kept.

She described P as being detained at the placement after 8pm, contrary to his wishes and feelings: “He was used to going out at home. He’s finding it very difficult to be confined to H premises after 8pm. That’s one of the reasons I think he is deprived of liberty”.

Her concern was not simply that P had fewer opportunities to go out. She argued that the restrictions could lead to distress, which in turn could result in behaviour that harmed others and made restraint more likely.

She also described what she saw as a lack of meaningful evening activity. From 8pm until he fell asleep, she said, P has little stimulation and is confined to a small bedroom using his iPad. Staff put him into his pyjamas from 8pm in preparation for the overnight staff. By contrast, she said, she tries to take him out after 8pm when she can: “Recently we’ve been to the theatre. And on short breaks, when I take him out, we have evening activities. That’s when I say he thrives. He’s treated like a 25-year-old and not a 5-year-old who can’t go out after 8pm”.

Her account presented the evening curfew not merely as limits on P’s movements, but as restrictions she believed were inconsistent with his established way of life and had adverse consequences for his wellbeing and behaviour – sufficient to constitute a deprivation of liberty.

Finally – the contact restrictions. The contact restrictions in the Schedule of Agreement arose in a different context from the question of deprivation of liberty: the discussion concerned whether P’s mother would continue to agree to the Schedule. Their impact on P’s mother is relevant context, but it’s not necessarily the case that restrictions on her contact with P automatically establish that P is deprived of his liberty. Nonetheless, since the Official Solicitor had just identified the Schedule as one element of the overall arrangements the court should consider in making a determination as to whether or not P is deprived of his liberty, I listened to the mother’s submissions with that in mind.

P’s mother said that she was “banned from his home” and therefore had to take P out whenever she wants to spend time with him. This means spending the whole day with him in the community on Wednesdays and half a day on Sundays – arrangements she described as exhausting.

She explained that she had chosen supported living for P because she had become “burnt out” caring for him herself. She now feels that the ICB and care providers have placed her in an “unsustainable situation”, without flexibility over when she can see her son.

Alongside a full-time job and her own health issues, the arrangements have become difficult to maintain. Because she spends Wednesdays with P, she has to work on Saturdays, and she is also struggling to visit him every Sunday. She wants  greater flexibility and the freedom to visit him in his own home.[10]

Her account illustrated how the Schedule affected not only the practical arrangements for family contact, but also her ability to sustain her relationship with P. The significance of those restrictions for the legal question of deprivation of liberty was a matter for the court to assess as part of the overall circumstances.

Position of P’s father: P is not deprived of his liberty

P’s father, representing himself, initially said that he agreed with both the ICB and the Official Solicitor.  When the judge pointed out that they had taken opposing positions, he said that he would leave the lawyers to address the legal question of deprivation of liberty.

He did, however, offer his perspective on the restrictions imposed on P: “a lot of the restrictions that are being defined as deprivation of liberty are there for his safety. It doesn’t mean they are holding him prisoner. They are there for a reason”.

His submission emphasised the protective purpose of the restrictions. Whether that purpose answered the legal question was for the court to determine.

Judgment

After a recess for lunch, the judge returned to deliver her judgment. She set out the factual background to the case and summarised, in neutral terms, the opposing arguments made by the ICB and the Official Solicitor with respect to whether or not P is deprived of his liberty. She continued:“I go back to the evidence given by P’s mother today before me. I found that evidence to be compelling. She was not involved in the incident on 4th July and didn’t know about it until she read about it in the notes. It rang a chord with her because she knows her son is frustrated by not going out at night. I have heard that he is put in pyjamas at 8pm. On that date he was told he couldn’t go out, and he became agitated. That is clear evidence of a deprivation of liberty.”

The judge then considered the restrictions on P’s daily life more broadly. “When the court looks at the Guidance from the DHSC, […] find externally imposed restrictions […] there are locked doors, 1:1 or 2:1 supervision – which is essential for his needs, even when he’s with his mother – no independent community access, and supervision for medication and personal care. There’s also restraint – as a last resort, but it is there – and there are restrictions on his contact with his mother via the Schedule of Agreement. Finally, his finances are managed by his mother and not by himself[11].  The building is always locked externally. He lives behind locked doors. The premises are small, and become smaller still by the presence of carers. He is confined […]. So, the court decides that P is currently subject to a deprivation of liberty. There is a clear absence of valid consent.” 

The judge therefore found that P’s arrangements amounted to a deprivation of liberty and that there was no valid consent. She went on to approve the deprivation of liberty as necessary, proportionate and in P’s best interests.

Reflections

One interpretation of the Supreme Court’s judgment in AGNI was expressed by DJ Glassbrook at another hearing in a different case: “The Supreme Court said that if there are objections then, on the face of it, we’ve got deprivation of liberty”.[12] 

This is an interpretation we’re seeing quite frequently. The judgment in P’s case might be read as supporting it. P’s distress on 4th July 2026, expressed through agitation and biting another resident when he was not allowed to go out was described by the judge as “compelling” evidence for a deprivation of liberty. The locked doors, continuous supervision, restrictions on independent access to the community, and restraint formed part of the wider  picture.

The judge’s reasoning, as recorded in the judgment, does not expressly explain how she weighed the incident of 4th July against the evidence advanced by the ICB that P “enjoys living where he is and he is thriving and happy there” — a view also supported by his father. The ICB relied on this evidence in arguing that P accepted his living arrangements and that there was valid consent.

The judge clearly attached considerable weight to the evidence highlighted by P’s mother: an occasion when P was prevented from going out, became distressed and was restrained. Her conclusion was that this was evidence of deprivation of liberty and that there was no valid consent. But I was left wondering how she reconciled that conclusion with the evidence of P’s general happiness at the placement. Did she regard the incident as revealing something fundamental about P’s experience of the restrictions, notwithstanding his otherwise positive response to his home? Or did she give it particular weight because it was a concrete example of what happened when P’s wishes appeared to conflict with the care arrangements? The judgment does not expressly resolve those questions.

Neither of the represented parties referred in their oral submissions to case law other than AGNI.  I was nevertheless struck by some similarities between this case and Re AR (Whether restrictions amount to a deprivation of liberty) [2026] EWCOP 45 (T2), heard by HHJ Burrows about a month earlier.  HHJ Burrows judgment is worth a read in conjunction with thinking about this case, since he’s a Tier 2 judge with considerable COP experience (and also appeared in Cheshire West), and was recently described by 39 Essex Chambers as  “…undoubtedly taking the lead as regards the development of a body of judicial consideration of the world after AGNI“.

Like P, AR is also a young man in his 20s with autism and a severe learning disability. He too had lived in the family home until moving, as a young adult, into his current placement.  Both cases also involve restrictions on contact with family members. In Re AR, as in the case reported in this blog post,  staff had expressed concern about visits that were late or cancelled at short notice, which they described as “unsettling” for AR.

But HHJ Burrows concluded that AR was NOT deprived of his liberty and he listed the following matters as decisive:

(a) AR suffers from a condition that will always require a significant level of supervision. There is a need in his case to ensure a good level of routine and predictability so as to ensure his relative happiness.

(b) AR will always require restrictions on his movement. He will never be “free to leave” wherever he safely resides, and significant control has to be placed on his movements in and out of his residence.

(c) Management of his behaviour will always require a high level of supervision and control, including when necessary, restraint.

(d) Although he is not at his family home, he is at a place which he is able to treat as his own and to personalise his environment. He is able to make friends, and engage in activities in and out of the placement.

(e) These restrictions are in place for his own good, and are intended to ensure the best outcome for him.

(f) Although his residence at the placement involves restrictions, they are far away from the paradigm of the prisoner in his cell, or, for that matter the mental patient in his secure unit.

(g) These arrangements are relatively normal.

I am struck by how many of these observations could be made equally about P. Like AR, P requires substantial supervision; his movements will always need to be restricted for his safety; managing his behaviour will also need a high degree of supervision – with restraint  available as a last resort; he has relationships with others at the placement and takes part in activities (swimming and trampolining were both mentioned); and the restrictions are to protect his wellbeing. Yet DJ Callaghan reached the opposite conclusion: P is deprived of his liberty.

The comparison raises a question about the significance attached to P’s distressed response to the evening restriction, and the resulting restraint. On the material I have described, this appears to be one of the most significant points of difference between the reasoning in the two cases. But it is difficult to assess precisely how much it explains the different outcomes without a fuller account of the reasoning in each judgment (particularly DJ Callaghan’s).

Contact restrictions provide another point of comparison. In Re AR, the parents were permitted supervised contact (only), with their son at his placement on the second and last Wednesday of each month — a more restrictive arrangement than the contact schedule described in P’s case.

HHJ Burrows recognised that contact could be a “significant” factor in determining whether a person was deprived of liberty. He observed that: “There may be situations where restrictions on contact with friends and family may be such as to change the character of the placement away from a home and closer to a place of detention”. But he concluded of AR’s circumstances: “This is, in my judgment, not one of them” (§67, Re AR).

The two judgments therefore leave me with a question. If the restrictions on movement, the need for supervision and the restrictions on family contact can be consistent with a finding of no deprivation of liberty in one case, but amount to a deprivation of liberty in another, what is it about the person’s experience of those arrangements that tips the balance?

The only explanation I can come up with is the weight attached to P’s response to being prevented from going out in the evening. DJ Callaghan treated the incident as “compelling” evidence of deprivation of liberty. But the precise role played by that evidence in the overall assessment is not fully explained in the reasoning available to me from the ex tempore judgment.

This matters beyond these two cases. AGNI requires a multi-factorial assessment that (where possible) takes seriously the individual’s own experience of their circumstances. But where the balance between the factors is decisive, transparency about how the court weighs them becomes especially important. Without that explanation, it is difficult for observers to understand whether different outcomes reflect meaningful differences in the evidence and the individual’s experience, or different approaches to applying the same legal test.

Celia Kitzinger is co-director of the Open Justice Court of Protection Project. She is on LinkedIn (here), and also on X (@KitzingerCelia) and Bluesky (@kitzingercelia.bsky.social)

Postscript: A transparency concern that listings never include “Is P deprived of liberty following AGNI” as a matter before the court

The public listing of this case appeared in CourtServe (the only way we normally get to learn about court hearings) as below.  The public listing said the hearing was about “WHERE P SHOULD LIVE & HEALTHCARE”. 
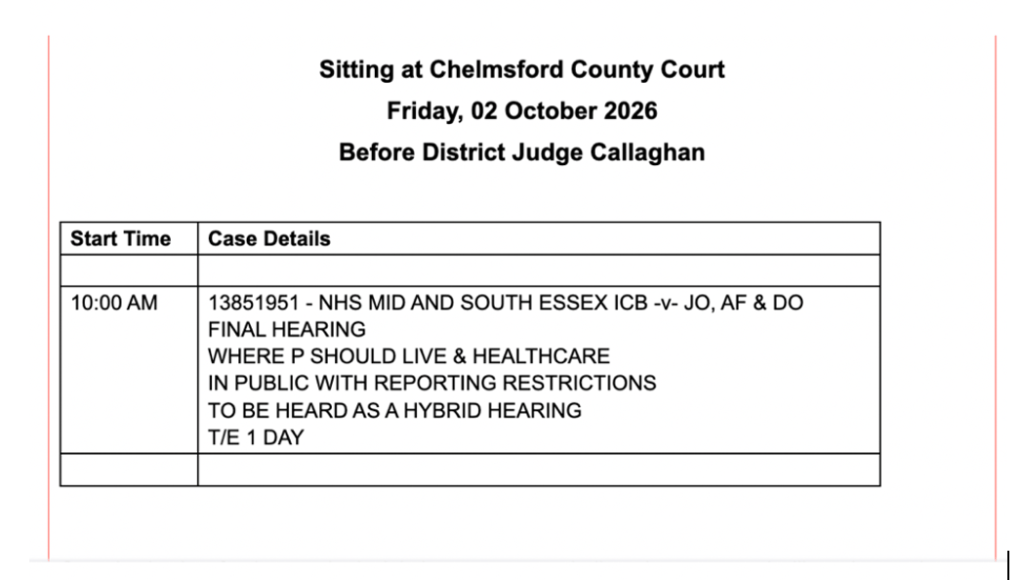
In fact, the matters before the court for this hearing were:

  • whether P is deprived of his liberty following AGNI;
  • whether to make a final best interests decision in respect of P’s residence (in the context of there being no available options) or whether, as P’s mother wanted, to keep proceedings live and direct the ICB to file evidence about potential alternatives
  • whether or not the “Schedule of Agreement” (contract of expectations) to which P’s mother had earlier agreed (meaning that an injunction with a penal notice against her had been discharged) should also now be discharged, since she objected to it (in which case the ICB intended to make a new application for an injunction)

We knew in advance, from observing an earlier hearing in this case (on 31st October 2025), that the listing did not accurately reflect the issues the judge would be asked to address today.  The question of “WHERE P SHOULD LIVE & HEALTHCARE” relates to matters from much earlier in the proceedings (which commenced on 5th November 2025) and does not reflect more recent developments.  Although the question of whether or not P was deprived of his liberty was the matter that occupied most of the court’s time, the phrase “deprivation of liberty” does not appear in the listing, and no member of the public for whom this was a compelling concern could have known from the public listing that this would be an interesting hearing to watch.

Conversely, I have selected and asked to observe hearings listed as being concerned with “deprivation of liberty” only to find, when I enter the courtroom, that in fact that is not an issue the court is concerned with that day.

Given the extent of legitimate public interest about the implications of the Supreme Court decision in AGNI for vulnerable people, and the way in which AGNI is being implemented in the Court of Protection, it is a significant problem for transparency  that court listings prevent us from accurately identifying those hearings at which the relevant issues will be aired in court.

Endnotes


[1] We’ve not blogged most of these cases (for reasons explained in the next paragraph of the main text), but links to those we have published about are available here: https://openjusticecourtofprotection.org/dol-in-the-cop-post-agni/

[2] In most cases, the person’s deprivation of liberty safeguards are removed without a court application in advance of, or immediately following, the next scheduled annual review process, as described by Joe and Sandra Preston in relation to their mother(-in-law) here: The irony and the AGNI.  No court application is required.  My own family is expecting the same to happen to our sister Polly: Polly and AGNI.

[3] I’m aware of only five published Court of Protection judgments, three of them by HHJ Burrows. They are: Oxfordshire County Council v P & G [2026] EWCOP 33 (T2); Re AR (Whether restrictions amount to a deprivation of liberty) [2026] EWCOP 45 (T2); Derby City Council v SM [2026] EWCOP 46 (T2); Re BM (Deprivation of Liberty) [2026] EWCOP 48 (T2) and Re PK & MK (Article 8 protections) [2026] EWCOP 52 (T2) – the last of these published subsequent to the date of this hearing. Additionally, two post-AGNI decisions about deprivation of liberty have been published by the Family Division: Re Mustafa (A Child) [2026] EWHC 2159 (Fam) and Essex County Council v MH, GH and ST [2026] EWHC 2328 (Fam). (There’s a helpful blog post about the two Family Division decisions here: “What do recent cases tell us about AGNI and deprivation of liberty for children and young people?”)

[4] I am grateful to the ICB’s legal team for preparing very helpful ‘Gardner documents’ (a case summary, list of issues and chronology) which have assisted in the accurate presentation of this case. I did ask for the Position Statements too, but they were not provided which means that I rely on the oral arguments alone in presenting the parties’ positions on how P’s care and residence arrangements do or do not constitute a deprivation of liberty.  In presenting these arguments I have drawn on my contemporaneous touch-typed notes and they are as accurate as I can make them, but unlikely to be verbatim. (The same applies to the ex tempore judgment of course.)

[5] There is a longer history to the proceedings, going back to January 2023 when the ICB initially sought authorisation of P’s care and support arrangements as a deprivation of liberty (approved in mid-October 2023) and made an order providing that annual renew of future deprivation of liberty authorisations would be via the streamlined Re X procedure.  Given what the ICB describes as ongoing  “strained” relationships and “difficulties and differences of opinion” between P’s mother on the one hand, and the ICB and care providers on the other, the Re X streamlined procedure was not appropriate in 2024.  In particular, P’s mother was disputing that P’s continued deprivation of liberty at H House was in his best interests.

[6] The specific incident P’s mother referred to was an occasion when P, visiting her at home was clearly in abdominal pain and “passed a stool with blue and white material in it”. She said she contacted the Deputy Manager and asked if they knew if P had swallowed something blue. They said not, but in her role as financial appointee she is given P’s receipts and found that he had been bought blue balls – and then later informed that he had a ball that he’d broken into small pieces but that staff had hoovered it all up. She referred the judge to a photo in the bundle – I think it was a sample of P’s stool which she had passed to the carers, who had assured her they would get it tested, but did not.

[7] The final hearing was initially listed for 4th March 2026. Rather than conclude the proceedings, the court directed the ICB to provide further evidence, which I understand concerned possible alternative placements. The seven-month delay before the final hearing in October appears to have had several contributing factors, including the need for further or better evidence about capacity, the parties’ inability to agree an order, the father’s unavailability on one of the dates initially listed for a final hearing, and a lack of confirmation from the court about subsequent hearing dates.

[8] Thank you to Claire Martin and Kim Dodd who both observed the hearing on 31st October 2025 and contributed to this blog post by checking my understanding of events before the hearing which I’m reporting on here.

[9] It seems there was a 1500-page bundle which the judge had only received around 8.30pm the night before the hearing, plus two supplementary bundles, each of 34 pages. This was, as the judge said, “unsatisfactory” for a final hearing. It was not, as I understand it, the fault of the parties: “I lay it squarely on the administration of the Court of Protection” (said the judge), saying that there was “only one admin officer actually doing any work in the building” when she called to ask for the bundle the day before.

[10] The judge did not make a ruling about this in her judgment – she simply encouraged “dialogue” about the arrangements but made clear that “what is important is that this placement is never undermined”. When subsequently asked by P’s mother about this – she expressed the view that flexibility would be desirable and made some suggestions about how that could work, saying: “this is a discussion I hope you’ll have with the ICB and the service provider”.

[11] The mother is P’s DWP and personal health budget appointee. In my view this is not, on its own, an obvious indicator of confinement, but it had been raised as such by the Official Solicitor.

[12] There is no published judgment. This quotation comes from a blog post: ” Objections (and breached conditions) after AGNI

 

After AGNI, are local authorities attempting to conclude proceedings inappropriately?

By Maria Maier, 6th October 2026

In this case (COP 14053038), the Supreme Court judgment intended to clarify when a person is deprived of their liberty (A Reference by the Attorney General for Northern Ireland (Deprivation of Liberty) [2026] UKSC 16, or “AGNI” for short) was used by a local authority as a reason for ending Court of Protection proceedings – prematurely, in the view of the judge. 

The hearing I observed (in person) was before DJ Reeder sitting at First Avenue House on 2nd October 2026 . Proceedings began in early September 2025, and this was the third hearing in the case (the first was listed – according to the Transparency Order – for October 2025) and the first I observed.

The Local Authority argued that, following AGNI,  the protected party (P) is not deprived of his liberty and that proceedings should therefore conclude. 

But as the hearing unfolded, the judge repeatedly found a striking disconnect between P’s care plan and what is actually happening on the ground.

For P, the reality appears to include both physical and chemical restraint. Yet neither is properly reflected in the care plan. 

As a result, the judge found himself unable to address whether or not P meets the post-AGNI test for deprivation of liberty because he first needs to understand the restrictions P is actually experiencing.

Observing in person

Knowing I had a relatively free day on 2nd October 2026, I checked the First Avenue House listings the evening before and saw three DoLS hearings listed before Tribunal Judge Reeder. I arrived in time for the 10:30am hearing, only to learn it had been vacated. I was advised that the 1pm hearing was likely to proceed, so I returned at 12:35pm and was given a copy of the Transparency Order to read.

On entering the courtroom, Tribunal Judge Reeder asked me to confirm that I had read and understood the Order, particularly the serious consequences of breaching it. He then introduced counsel. The applicant was initially P’s brother (and financial deputy) who is a litigant in person, however I am unsure whether he remains the formal applicant or has been replaced by the Local Authority. The Local Authority (the London Borough of Harrow) was represented by Michael Paget of Cornerstone Barristers. The protected party (P) is a respondent in these proceedings represented, through the Official Solicitor, by Alex Cisneros of 39 Essex Chambers. The judge then helpfully asked Mr Paget to provide a summary of the case for my benefit.

The hearing

The hearing concerned a young man (P) who lacks capacity to make decisions about his care and residence and lives at home with his family. 

The proceedings began in September 2025, after P’s brother asked the Court to determine whether P required a DoLS authorisation at the family home. His application preceded the Supreme Court’s decision in AGNI.

At a hearing after the AGNI decision was handed down, the parties disagreed about whether the restrictions placed on P amounted to a deprivation of liberty and the Court directed the parties to provide updated evidence for the court to make a determination on this. That was the issue before the court for the hearing I observed.

At this hearing, on 2nd October 2026, the Local Authority’s position was that P was not deprived of his liberty under the new AGNI test and that it is in his best interests to remain living at home. It therefore sought a declaration that P should continue to live at home and attend his day centre, with everyone following the existing care plan. From the Local Authority’s perspective, there is no reason for the proceedings to continue.

The Official Solicitor took a different view, submitting that it remains unclear whether or not P’s restrictions amount to a deprivation of liberty under AGNI, particularly because there has not been sufficient recent evidence or opportunities to establish P’s current position.

The Judge began by questioning the Local Authority’s position. There is an overarching care plan for P at home and at his day centre, but the plan contains no provision for physical restraint. This is significant because, despite the absence of any such provision, P’s family have resorted to physically restraining him on regular occasions. Staff at his day centre are similarly not authorised to use physical restraint but they apparently do not do so: they rely instead on distraction and other techniques.

Judge Reeder identified the difficulties immediately: P spends his days at the day centre but is at home in the evenings and throughout the weekend, so  “the conundrum that is bothering me is that P has different sides to his life”. Moreover, the Judge continued: “Despite there being no proposal for physical restraint, the opposite seems to be true“.

He questioned how the court could conclude that P is not deprived of his liberty when physical restraint is actually being used, particularly when this appears to be happening at home without trained staff. He also raised the issue of chemical restraint, noting that P is taking antipsychotic medication but that there is no reference to chemical restraint in the care plan.

The Local Authority maintained that, although physical restraint had been used, it is not needed and is not authorised. When the Judge asked how physical restraint could be authorised if it did become necessary, Mr Paget explained that it would need to be included in the care plan, or in a Positive Behaviour Support plan, or another form of plan. There is, however, no such provision for P.

The Judge remained concerned. One of the most striking observations he made in the hearing was this: “What is happening on the ground is not what is being conveyed“.

He explained that he needed direct evidence from those providing P’s care before he could be satisfied that physical restraint is unnecessary. When the Local Authority attempted to rely on another document, the Judge was not satisfied that it reflected what is actually happening.

The judge’s frustration was evident: “I need to start drawing the line. These are personal welfare proceedings that began in September 2025. We need to understand what is actually happening and what is in the care plans“.

He noted that this was already the third hearing, yet the court was still trying to establish what was and was not happening in practice. Evidence from a care provider and an appropriate supervisor at the day centre is therefore required.

The Local Authority referred to advice given by a clinical psychologist in 2022, which had suggested using visual techniques to distract P and to avoid physical restraint. However, the Judge was not satisfied that this provided the answer. The evidence was four years old, and, after further discussion, the court found that the suggested techniques had not been adequately shared with P’s family.

The issue of chemical restraint then became more prominent. The Judge asked why the care plan made no reference to chemical restraint when P is taking three medications, each of which has sedative effects and has been prescribed for that purpose. He also asked where the medication is being administered. There was initially some confusion about whether medication is being given at the day centre, before P’s brother clarified that P receives the morning and evening dose at home, with the midday dose administered at the day centre and at a dosage which had been increased in January 2026.

The Judge then returned to the central difficulty. If P is in reality being physically and chemically restrained, while his care plan does not anticipate either form of restraint, how could the Court be satisfied that the arrangements represented the least restrictive option?

The Local Authority nevertheless maintained its position: P is not deprived of his liberty under AGNI and the proceedings should conclude.

Judge Reeder disagreed. He said that there is insufficient evidence to make that decision. He explained that he needed more information to make a best interests decision under section 4 of the Mental Capacity Act 2005 and to ensure that P was subject to the least restrictive option under section 1(6).

The Judge then asked P’s brother to explain what life actually looks like for P at home.

The brother’s evidence highlighted a stark difference between P’s two environments. At home, P lives in a three-bedroom house across three floors with various family members including his mother, sister and another brother with children. The brother, who had made the initial court application , described a recent incident in which P’s sister had woken P up to attend the day centre and he had attacked her, requiring P’s other brother to physically restrain him.

The day centre is very different. P has two-to-one male staff with him and access to several different support workers who use distraction techniques to calm P down. As his brother explained: “It’s a completely different space with different rules, people, equipment to distract him, that’s why they don’t need to use physical restraint and we do“.

He stressed that the family does not want to restrain P and that they regularly try other approaches first. Sometimes this means taking P out in the middle of the night simply to distract him, including driving to McDonald’s at 2am.

This evidence complicated the Local Authority’s suggestion that physical restraint simply should not be happening. It also demonstrated why the Judge was reluctant to determine the case based solely on the written care plan.

P’s brother would like P to move closer to him and requested an independent social worker to help develop a new care plan. He also described longer-term possibilities, including applying for housing in P’s own name, as well as seeking additional paid carers or financial support for family members to take more time to look after P. When asked whether the family would be willing to undertake additional training to best support P, he confirmed that they would.

The Judge made clear that he was not minded to conclude the proceedings that day. He remained concerned about the use of chemical restraint, the uncertainty surrounding physical restraint and, above all, the disconnect between P’s care plan and his actual life at home.

Counsel for P through the Official Solicitor identified the wider significance of the case: “One of the impacts of the AGNI decision is that it has led to Local Authorities attempting to conclude proceedings in inappropriate circumstances.”

The Judge agreed that the starting point had to be evidence “from the horse’s mouth”. He wanted evidence directly from the care service and someone in an appropriate supervisory position at the day centre. This evidence needs to explain what care plan or Positive Behaviour Support plan staff are following, how it is implemented, whether physical or chemical restraint is used often, what techniques are being employed and what threshold triggers escalation. He also wanted evidence about P’s behaviour and safety during transport to and from the day centre, as despite a safety lock and car seat, P had managed to jump out on a recent occasion.

The Judge also asked P’s brother to begin documenting P’s behaviour on a daily basis. He acknowledged the additional burden this placed on P’s family but emphasised the importance of obtaining evidence about P’s life at home. Judge Reeder did not prescribe a particular format but suggested keeping a diary recording episodes of challenging behaviour, the methods used to calm P, and any physical or chemical restraint used. He also requested a one-page spreadsheet setting out the payments made to P’s family and carers, leaving P’s brother and the Local Authority to decide who would provide the information.

The Judge concluded that the care plan itself needed to be reviewed and that the Court needed more “hard-edged evidence”.

Crucially, he made clear that he was not going to determine the AGNI issue (i.e. whether or not P was deprived of his liberty) on the evidence before him.

Instead, he directed the Local Authority to produce an updated version of the care plan and establish what P’s care and support arrangements would actually look like going forward. Until that evidence was available, the existing DoLS authorisation would continue.

The hearing concluded with directions for further evidence, including a statement from the Local Authority addressing physical restraint at home, behaviour and support plans, risk assessments and medication. The Court also sought a recent medication review, information about respite options and fuller consideration of alternative care and accommodation arrangements, including whether the current arrangements were sustainable or whether options such as co-living or weekend residence should be explored.

By the end of the hearing, the proceedings had not been concluded. Instead, the Court had identified significant gaps between the formal care plan and P’s lived reality and required the parties to provide evidence capable of resolving them. 

Reflections

I was struck by Mr Cisneros’ observation that one impact of AGNI has been that local authorities are attempting to conclude proceedings in inappropriate circumstances. This confirmed a worry that I had as an RPR, as I saw a sharp reduction in DoLS authorisations – and therefore in access to independent advocacy support – in the months immediately following AGNI. I was particularly surprised that this case was considered capable of ending when there were still significant questions about what was happening to P.

It was fortunate that the case was already before the Court. Judge Reeder was able to scrutinise the LA’s position and identify the gap between P’s care plan and his life in practice. However, this made me wonder how many people may be left without the same scrutiny if an LA concludes that there is no longer a deprivation of liberty and proceedings are not brought before the Court. It should not require family members (like the brother in this case) to make applications for a deprivation of liberty to be properly identified.

The hearing also highlighted the importance of clear, direct evidence. Even at the third hearing, the parties were still trying to establish what was actually happening to P. The Judge’s insistence on evidence “from the horse’s mouth” showed how difficult it is for the Court to make decisions about a person’s welfare when the care plan does not reflect their lived reality. 

As an observer, I found the hearing particularly easy to follow. The Transparency Order was provided on arrival, the Judge gave a clear summary of the case, and all parties spoke slowly and clearly. This made the proceedings accessible not only to me, but also to P’s brother as a family member and litigant in person. .

Maria Maier is an aspiring barrister. She previously worked as a Relevant Person’s Representative (RPR) and Rule 1.2 Representative for adults who lack mental capacity and are deprived of their liberty under the Mental Capacity Act (MCA) and she’s published other blogs for the Project. She began her Bar Course studies in September 2026 at the Inn’s of Court College of Advocacy. Her LinkedIn is here.

No public admittance to a ‘public’ post-AGNI hearing before HHJ Burrows

By Claire Martin, 27th September 2026

It goes without saying that hearings listed as ‘public’ should be accessible for members of the public to observe. Especially when they relate – as so many Court of Protection hearings do – to deprivation of liberty for vulnerable people. I was especially interested in this hearing before HHJ Burrows, who has something of a reputation as a judge making important decisions in this area. Another blog post covers HHJ Burrows’ ex tempore decision-making (there’s no published judgment) back in June 2026 in relation to a woman with profound disabilities living in an annex to her family home (“Considering ‘deprivation of liberty’ in a family home setting after AGNI“), and since the events described in this blog post, HHJ Burrows has published one of the first reported judgments to apply the new multi-factorial AGNI test (Re AR (Whether restrictions amount to a deprivation of liberty) [2026] EWCOP 45 (T2)).

So, I was frustrated and disappointed not to have been able to observe a remote hearing listed before HHJ Burrows in Preston on Monday 3 August 2026. I couldn’t observe it because I was never sent a link. Despite chasing repeatedly, I never received any reply at all. This was a fully remote hearing – so without the link, there was no way of observing it. Without the link, it wasn’t, in reality, “public” at all.

Background

There are two parts to the ‘background’ of what happened in relation to this hearing. I’ll deal first with the rules about remote observation and then the legitimate public interest in ‘deprivation of liberty’ hearings post-AGNI, which motivated my request to observe this (fully remote) hearing.

Remote observation of fully remote hearings

Those of us involved in the Open Justice Court of Protection Project have observed many remote hearings. Most of our blog posts concern hearings attended not in person but remotely – including hearings that took place in person (with a remote link provided for observers), as well as “hybrid” hearings (an in person hearing with one or more parties or their representatives attending remotely). But in most cases, the hearings we observe remotely are fully remote. That means there is nobody – except perhaps the judge – sitting in a physical courtroom: the only way of observing is via the link.[1]

Remote access to a public hearing is not a “right”[2]. Before making a direction to send a link to an observer, the court must be satisfied that (a) it would be in the interests of justice to make that direction; and (b) there is capacity and technological capability to enable transmission and giving effect to the direction would not create an unreasonable administrative burden. A list of mandatory considerations includes the need for open justice, the timing of any access request and its impact on the business of the court; the  extent to which the resources necessary for effective remote observation are or can be made available; and any impact which the making or withholding of such a direction, or its terms, might have upon (i) the content and quality of the evidence; (ii) public understanding; (iii) the ability of the media and public to observe and scrutinise; and (iv) the safety and right to privacy of any person involved with the proceedings.[3]

The rules do not seem to differentiate between public hearings which are taking place “in person” (so that, at least in principle, an observer could go along to a physical courtroom), and those that are fully “remote” – meaning that everyone is online. Counsel and judges in fully remote hearings are usually in their place of work, but sometimes at home or in another location, and the judge may or may not be in a physical courtroom – and if they are, it may not be the court in which they are formally sitting. Especially during the COVID-19 lockdowns, but also subsequently, we’ve seen judges ‘sitting’ in the Court of Protection from home, in hotels, and even while on holiday. The transparency problem with wholly remote hearings is that if a link is not sent, then there’s – usually – no physical location to which we can go to observe the hearing, in which case it’s hard to see how they can be understood to be “public”.

Public interest: the Supreme Court decision in AGNI

On 2 June 2026, the UK Supreme Court handed down judgment in the case now often referred to as AGNI (formally known by the distinctly un-catchy title “A Reference by the Attorney General for Northern Ireland of a devolution issue under paragraph 34 of Schedule 10 to the Northern Ireland Act 1998 UKSC/0042). In that judgment, the Supreme Court overturned Cheshire West, thereby upending over a decade of practice in this area. We have published multiple blogs about the hearing and judgment here: Commentary on the UK Supreme Court case about deprivation of liberty, and also blogs about subsequent cases where judges have considered the AGNI ruling in relation to deprivation of liberty cases in the Court of Protection (Deprivation of Liberty in the CoP post-AGNI).

Deprivation of liberty cases are a large part of the work of the Court of Protection. The Family Court Statistics Quarterly (Jan-March 2025) reports that there were 2,127 applications relating to deprivation of liberty in January – March 2025, amounting to 23% of the application made under the Mental Capacity Act in that quarter. But there are very few published judgments concerning deprivation of liberty, post-AGNI. To date, there have been two from the Court of Protection (here and here ) and one from the Family Division of the High Court (here).

Deprivation of the liberty of citizens in England and Wales is of considerable legitimate public interest. The core team of the OJCOP Project and other public observers have been endeavouring to observe hearings concerning deprivation of liberty, post-AGNI, to understand how the Supreme Court ruling is being interpreted and implemented in case law.

My request for the link was ignored

The hearing of Case 20035953 was listed as “public”. I emailed the evening before requesting link, Transparency Order and Position Statements (or Gardner Documents). I couldn’t email any earlier than this because the listings are not published until around 4.30pm the day before a hearing. This is often not understood by judges, who can, consequently, feel frustrated to receive a request from a public observer quite close to the start time of a hearing. It’s an issue we have raised many times but is intractable because of the dynamic nature of cases coming to court. Balancing open justice with other administrative pressures can be difficult and is one of the reasons why access to links is within the judge’s discretion according to the “Practice Guidance on Remote Observation of Hearings”. I don’t dispute the administrative pressures on the court – they are everywhere apparent – but I am concerned about their consequences.

This is the email I sent to the Manchester hub (whose email is provided in the listing):

The hearing was listed to start at 10am. As it approached 9.30am, having received no acknowledgment of my email and no link to observe, I decided to resend my email with the note as below, which was sent time-stamped at 9:24am.

At 9.48am, I had still not heard from the court hub in Manchester so I telephoned the generic 0300 number provided in the listing above. There were what felt like endless recorded voice messages, which were not relevant to the matter I was dealing with and frustrating to listen to, as I was aware that the hearing started in 12 minutes.

I have been reprimanded in public, several times, by judges annoyed that I have asked for the link ‘late’ or joined the link ‘late’ (e.g. see this blog: Why members of the public don’t ask earlier to observe hearings (and what to do about it)). This is always outside of my control and it feels particularly unpleasant and unfair to be treated this way when a hearing is listed as ‘public’ and we observers cannot request links any sooner than the evening before (i.e. at a time when court staff have usually gone home, meaning they will need to respond first thing in the morning). Of course, this is difficult for court staff too, but that’s the system we are all faced with currently and it is very rarely the fault of the observer for asking or arriving ‘late’. This was all on my mind when I was faced with silence from the Manchester Court of Protection hub.

The recorded messages were mostly about travelling to court. I couldn’t bypass them and had to sit through them all to reach the number options to take me to another portal.

I finally got to an option saying: ‘if your query is about a hearing in the next 24 hours’ – I ‘held’ (as advised, to enable me to speak to someone) and it told me I was in a queue. The messages are long and not always understandable – e.g. if I want to complete a survey about my experience press 1, if not please hold and we will forward your call to a member of our team. Does that mean I can’t both ‘complete a survey about my experience’ and ‘speak to a member of [the] team’?

I was still on hold at 9:52am. There was annoying floaty music. The hearing was now due to start in 8 minutes.

‘One of our call agents will be with you shortly. Thank you for your patience’. I wasn’t feeling particularly patient at this point.

‘Did you know you can find further information on our processes on www.gov.uk’.

Floaty music.

9:55 ‘One of our call agents will be with you shortly’

Then the phone call was cut off at 10:02am.

The hearing was likely to have started two minutes earlier.

In one last attempt to gain access to this purportedly public hearing, I emailed Preston Family Court directly at 10:04am. I know we’re not supposed to contact the local court but we’ve discovered sometimes that’s the only thing that works – though it didn’t work this time.

I have never received an acknowledgement or reply to any of my emails.

The obvious questions are ‘what went wrong?” and ‘what should be done about it?’. I’ve told the story from my perspective and don’t feel able to say much else about this situation really – except to add that it’s not uncommon for public observers to find themselves in this situation. That’s why I’ve taken the step of writing about it. Most people don’t because they feel – reasonably enough – that they’ve already wasted enough time trying to get access to a purportedly “public” hearing and writing about it is likely to be more wasted time. I’m sure if I contacted the court I’d be told (as observers have before) that it was a particularly difficult morning, staff were very stretched, or someone was off sick, or a new member of staff was in need of further training. I don’t doubt that those things are often true. But the consequence is that ‘public’ hearings are actually heard in private and the judicial aspiration for transparency is thwarted.

Maybe the open justice champions heralded by Mr Justice Nicklin in June 2025 (reported by  the Law Gazette here) could start to address this. In his speech in June 2025, Mr Justice Nicklin (referring to the Transparency & Open Justice Board), said: ‘The board and HMCTS are aware that there can be issues with people gaining timely access to remote hearings’, Nicklin said. ‘HMCTS are working to provide “open justice champions”. They will be regionally based, and it is intended that they will provide a single point of contact to assist in resolving open justice issues.’ We will see, once they are in place, whether open justice champions can make a difference.

A fully remote hearing is not “public” if the public cannot obtain links. Despite claiming otherwise, this hearing simply wasn’t, in reality, a public hearing. If the resources are not available to provide a link for observers for a fully remote hearing then the hearing is effectively “private” and would be better listed as such. Listing these effectively private hearings as “public” creates a misleading impression of transparency in the Court of Protection. And it’s particularly disappointing when the issue before the court is such an important matter of legitimate public interest (deprivation of liberty) and it’s being heard by an influential judge.

Claire Martin is Lead Consultant Clinical Psychologist, Cumbria, Northumberland, Tyne and Wear NHS Foundation Trust, Older People’s Clinical Psychology Department, Newcastle-upon-Tyne. She is a member of the core team of the Open Justice Court of Protection Project and has published dozens of blog posts for the Project about hearings she’s observed (e.g. here and here). She is on X as @DocCMartin, on LinkedIn and on BlueSky as @doccmartin.bsky.social

Endnotes


[1] This has posed a problem for transparency when cases listed as “in person” are changed at the last minute to remote hearings.  See ‘Observing a remote hearing in court with the judge” which describes a situation in which only the observer and the judge were in the physical courtroom, with everyone else on line for what had been “rejigged as an MS Teams hearing” late in the day.  In another case (also before HHJ Hilder) where two observers turned up at First Avenue House what was listed as an “in person” hearing, they was seated in a consultation room with a laptop and supported to observe the hearing (taking place just down the corridor) remotely.

[2] The statutory power to admit members of the public to observe remote hearings lies with  section 85A of the Courts Act 2003 as inserted by section 198 of the Police, Crime, Sentencing and Courts Act 2022. The regime is implemented by the Remote Observation and Recording (Courts and Tribunals) Regulations 2022. 

[3] “Practice Guidance on Remote Observation of Hearings”

“Wrapped in Cotton Wool”: Protection, Restriction and P’s Best Interests

By Layba Khan, 3rd September 2026

Every parent wants to protect their child. Yet there comes a point where protection itself may become restrictive. This tension lay at the heart of a case (COP 20033356) I observed on 25th June 2026 before Mr Justice Hayden, sitting in the Royal Courts of Justice.

Following years of serious illness, the parents of the protected party (“P”) in this case had created what the judge described as a “cocoon of happiness” around their daughter. The difficult question before the court was whether preserving that cocoon truly served P’s best interests or whether accepting the risks of elective surgery could offer her the opportunity for a fuller and less restricted life.

I observed this hearing as part of my LLM pro bono project. Mental capacity law is an area in which I have a particular interest; during my LLB, I was awarded the Mental Health and Mental Capacity Law Subject Award. I was therefore particularly interested in seeing how the principles I had studied were applied in practice, especially in a case where there was no straightforward right or wrong answer and where medical evidence, the views of those involved, and P’s welfare all had to be carefully considered.

I’ve previously observed a sexual offence trial in the Crown Court in Leeds. Both hearings involved the consideration of evidence, legal submissions and careful judicial scrutiny, but the purpose of the proceedings was very different. The sexual offence trial focused on determining whether the prosecution had proved the alleged offence beyond reasonable doubt, whereas this hearing focused on P’s capacity to make a particular decision and, if she lacked capacity, what decision would be in her best interests. I found this particularly valuable because it showed me how judicial decision-making can differ depending on the nature of the proceedings.

My interest in the hearing was also informed by my part-time work supporting university students with disabilities. This role has given me experience of working alongside students with a range of support needs and has reinforced the importance of treating each individual as a person rather than simply focusing on their disability. I hoped that observing the hearing would allow me to better understand how these principles are reflected in practice within the Court of Protection, and how the court seeks to ensure that the individual remains at the centre of its decision-making.

Background

The hearing concerned a 24-year-old woman (“P”) with Down syndrome, a learning disability and severe Crohn’s disease. The NHS Trust (Nottingham University NHS Foundation Trust) sought declarations that P lacks capacity to decide whether to undergo further bowel surgery, and, if so, that the proposed elective procedure was in her best interests.

Counsel for the Trust was Ms Taylor (I have been unable to establish which Ms Taylor this was). The protected party was represented by the Official Solicitor as her litigation friend, with Ms Emma Sutton KC as counsel. P’s parents were parties to the proceedings as the second and third respondents and appeared to be acting as litigants in person, addressing the judge directly during the hearing. The seven-hour hearing brought together expert medical opinion, judicial scrutiny and the deeply heartfelt contributions of P’s parents. At its core, the court was required to balance the significant risks of surgery against the potentially life-threatening consequences of allowing the disease to continue untreated.

P is the youngest of three children and had previously enjoyed an active life before suffering an emergency bowel perforation in 2023. She underwent several emergency operations, spent months in intensive care and, following her prolonged admission, had to relearn how to walk and speak. As a result of extensive bowel loss, P now lives with intestinal failure. She receives overnight parenteral nutrition through a central line and continues to live with a stoma requiring ongoing management.

Although she is able to eat small amounts of food during the day for comfort and enjoyment, this provides little nutritional benefit. Despite receiving maximal medical therapy, P’s Crohn’s disease remains active. Recent MRI scans showed ongoing inflammation and narrowing of the bowel, caused by a combination of disease activity and scar tissue formation. The narrowed section, known as a stricture, is already causing a partial obstruction. Whilst bowel contents can still pass through, clinicians warned that there remains a risk of complete obstruction or another perforation developing in the future.

Capacity and the Challenge of Discussing Treatment

Before considering the medical evidence, the court first had to determine whether P had the capacity to make the decision herself.

The consultant colorectal surgeon explained that P had been assessed with the support of a learning disability nurse. Despite appropriate adjustments designed to maximise her understanding, she was unable to understand, retain, use or weigh the information relevant to making a decision about undergoing surgery. The court accepted the evidence that P lacked capacity both to make decisions about the proposed operation and to conduct the litigation itself.

The evidence also illustrated the challenges clinicians encountered when discussing treatment with P. A patient with capacity would ordinarily receive detailed explanations of all material risks, including the risk of death, but P became distressed whenever surgery was discussed and frequently indicated that she no longer wished to engage in such conversation. The consultant explained that As a result of P’s distress, discussions had necessarily been adapted. The judge later observed that P had never been given the full range of information that would ordinarily be provided to a capacitous patient, particularly in relation to the potentially fatal consequences of declining surgery.

Stability or False Reassurance?

Much of the hearing focused on the apparent contradiction between P’s current stability and the recommendation for surgery.

The MRI scans appeared unchanged from imaging performed several months earlier. Counsel on behalf of P questioned whether the absence of significant progression suggested that surgery could safely be delayed. If P had remained stable for five or six months, why could that not continue for another five or six more months?

An independent expert, Dr W, accepted that the scans were reassuring to a degree. However, he cautioned against viewing the imaging in isolation. Scans, he explained, are snapshots in time rather than a complete account of disease progression. Whilst the visible changes over six months appeared modest, active inflammation remained present and, in his opinion, progression was inevitable. The difficulty was that no clinician could reliably predict when the progression would become clinically significant.

This disease could remain relatively unchanged for an extended period of time. Equally, a serious complication could develop before any obvious deterioration appeared on imaging. What Dr W repeatedly emphasised was that what appeared to be stability was not a true status quo. Rather, it was a temporary period of relative calm within a disease process that continued to worsen beneath the surface.

Why Operate Now?

For P’s parents, the prospect of surgery at this stage was particularly difficult to understand. Why now? Why not wait?

For the first time since P’s emergency admission in 2023, she appeared happier and more settled. She had enjoyed her longest period without hospital admission, had adapted to a predictable routine and was spending time doing things she actually enjoys, including listening to music, playing games on her iPad and interacting with her family. Her mother described this as the best year P had experienced since her illness dramatically worsened. To them, this felt like the worst possible moment to put P through another major operation.

To the clinicians, however, this period of relative wellness represented the safest opportunity to intervene before her condition deteriorated further. What P’s parents saw as a period of recovery, the medical team saw as a narrowing window in which surgery could be undertaken in a planned and controlled setting rather than during another life-threatening emergency. Elective surgery is generally safest when a patient is as fit and well as possible.

As the evidence developed, the experts returned repeatedly to the same principle: the question was not simply whether surgery carried risks, but whether delaying surgery carried even greater ones. Dr W described the danger of “missing the boat”.

The Case for Surgery

The Trust argued that maintaining the current position was not a sustainable option. While the proposed surgery undoubtedly carried significant risks, those risks had to be weighed against the consequences of doing nothing. P’s Crohn’s disease remained active despite maximal treatment and another bowel perforation was considered more likely than not. If that occurred, P would likely experience severe pain, widespread infection and peritonitis. Emergency surgery would carry substantially greater risks and might no longer be in her best interests, leaving palliative care as the only realistic option.

By contrast, if the surgery proved successful, there were a number of potential benefits. Most importantly, removing the diseased bowel segment would substantially reduce the risk of future perforation and obstruction. It would eliminate the section of bowel responsible for the ongoing inflammation and remove what clinicians described as the looming risk of a catastrophic event.

Dr W explained that the diseased segment of bowel was responsible for far more than simply creating a future risk of obstruction or perforation. In his opinion, it already posed a risk to P’s day-to-day wellbeing. The ongoing inflammation was contributing to pain, vomiting and restricted oral intake, whilst also causing the loss of protein, antibodies and immune cells through the bowel wall, resulting in reduced immunity, poor nutritional status and a general sense of ill health. The expectation was that removing the diseased section could improve these problems, lessening her reliance on immunosuppressive medication and potentially giving her greater freedom to leave the house and engage in everyday activities that she has increasingly been unable to enjoy. Although there could be no guarantee that P would ultimately become stoma-free, this remained a possibility depending on the findings during surgery and her subsequent recovery.

Food emerged as one of the most significant quality-of-life issues considered by the court. Given the restrictions imposed by her illness, P’s parents described how meals had become one of her greatest pleasures and a central feature of her family life. The judge acknowledged this, observing that food represented much more than nutrition. It is about enjoyment, family relationships and maintaining a sense of normality in her life.

The medical evidence suggested that, if surgery succeeded, P would be able to eat a wider variety of food without fear of pain, vomiting or obstruction. There may still be restrictions in the short term, particularly regarding fluid intake depending on how much bowel remained after surgery, but experts hoped she would ultimately experience greater dietary freedom than she currently enjoys. Importantly, eating would no longer be limited by the mechanical narrowing created by the stricture.

The Risks

The benefits, however, were never presented as guaranteed.

This was going to be a major abdominal surgery carrying significant risks, including serious complications and a measurable risk of death. The immediate recovery period would likely be difficult and prolonged. There was uncertainty regarding exactly how much bowel would need to be removed and the possibility that operative findings may differ from what the MRI scans suggested.

There were also concerns about the psychological impact for both P and her family of returning to hospital, particularly given the trauma associated with her emergency admission in 2023. Dr W was frank that any capacitous patient would have substantial reasons to think carefully before consenting to surgery of this nature. He repeatedly described the decision as delicately balanced, acknowledging both the potential gains and the significant burdens associated with the operation.

The Parents’ Perspective

Throughout the hearing, it was clear that P’s parents’ position was rooted not in distrust of the medical evidence but in the trauma they had experienced watching their daughter fight for her life.

P’s mother said that surgery offered no cure for Crohn’s disease and that recurrence remained possible. She described how P had finally reached a point where she seemed settled, genuinely happy again after years of illness and repeated hospital admissions. To her, the current period represented something precious that could easily be lost.

Throughout the hearing, P’s personality emerged vividly through the evidence. Her father described P as “the queen of the family”, a strong-minded young woman whose approval is still sought by her older brothers. Both her parents spoke of her love of music, her iPad, family interactions and her remarkable ability to adapt to circumstances that would overwhelm many people. Despite living with significant pain and restriction, she rarely complains and often apologises for the impact her illness has on others.

For P’s parents, preserving the quality of the life P currently enjoys was more important than pursuing an operation that carries no guarantee of success. They feared that another major procedure could leave her with further complications while destroying the stability she had only recently regained.

Mr Justice Hayden was clearly struck by their evidence. It was during this part of the hearing that the judge reflected on the delicate balance between protection and restriction. He observed that “wrapping someone in cotton wool” can itself become restrictive and acknowledged the difficulty of risking what he later described as the “cocoon of happiness” that P’s parents had created around their daughter. Nevertheless, he reminded the court that P was “an adult with adult rights” and that the court’s task was not merely to identify the safest option but to determine what outcome truly served P’s best interests.

The Judge’s Conclusion

Mr Justice Hayden ultimately found the evidence regarding the consequences of doing nothing particularly compelling.

The judge was also influenced by P’s personality and character. Having met her personally, he described a young woman who was resilient, sociable, determined and deeply engaged with the world around her despite the considerable restrictions imposed by her illness. He observed that P had never previously been given the opportunity to experience surgery specifically intended to improve her quality of life. Her previous operations had all been emergency, life-saving interventions undertaken in response to catastrophic deterioration rather than procedures aimed at addressing her Crohn’s disease and improving her long-term future.

In reaching his decision, the judge recognised that he was weighing two remarkably different futures. One involved undertaking major elective surgery now, while P was relatively well, accepting the immediate risks and uncertainties in the hope of improving both the quality of her life and potentially the length of her life. The evidence suggested that performing surgery now could allow clinicians to anticipate and plan for any future complications in a way that would simply not be possible during a future emergency admission. The alternative was to preserve the relative stability that P currently enjoyed.

Ultimately, Mr Justice Hayden accepted the medical evidence that this stability did not represent a genuine status quo. Rather, it exists within the context of a progressive disease carrying a substantial likelihood of obstruction, perforation, peritonitis, severe pain and potentially death. The evidence persuaded him that the real question was not whether serious complications would occur, but when. Against that backdrop, the proposed surgery offered P the possibility of a future less constrained by Crohn’s disease and one that she had never previously been given the chance to experience.

Perhaps the most poignant moment of the hearing came towards its conclusion. The parents acknowledged that they understood the medical evidence and recognised why the Trust believed surgery was the right course. Their difficulty was not in understanding the decision but in living with it. Having already watched their daughter come close to death once, they simply could not bring themselves to authorise another major operation and asked that responsibility rest with the court.

In deciding that elective surgery was in P’s best interests, the judge acknowledged the profound love and care shown by her parents but accepted the medical evidence that waiting would expose P to greater risks in the future. The court’s decision was based not only on the prospect of preserving P’s life but also on the possibility of reducing pain, increasing independence, expanding her diet, improving wellbeing and offering her opportunities that her illness currently denied her. In the end, the court concluded that preserving P’s current life and improving it were not necessarily the same thing. Whilst surgery carried immediate and significant risks, the evidence demonstrated that the apparent stability she currently enjoyed could not be expected to last indefinitely. The decision was therefore not about choosing between risk and safety, but about choosing between two uncertain futures. For the court, P’s best interests lay in giving her the opportunity to pursue the better one.

The judgment serves as a powerful reminder that best interests decisions are rarely about choosing between a good option and a bad one. More often, they require the court to navigate between two profoundly difficult paths. In B’s case, protecting her did not ultimately mean preserving the life she has today. It meant giving her the opportunity to have a better one tomorrow.

Layba Khan is a law graduate who has completed the Bar Practice Course and is currently undertaking an LLM in Law at the University of Law. She is an aspiring barrister with a particular interest in mental capacity and Court of Protection law. She can be found on LinkedIn here.

Editorial Note: This case was previously before Trowell J on 11th May 2026 – presumably for directions and case management prior to the final hearing reported in this blog post. At least two members of the public asked to observe the hearing on 11th May 2026 and were not sent the link in time for the start of the hearing. This was because the hearing had been wrongly displayed on the public lists (due to “administrative error”) to begin at 2.00pm. In fact the hearing started at 10.30am that morning. We’ve been told that the listing team have put a system in place to avoid a repeat of this kind of error – which obviously defeats the judicial aspiration for transparency.

“Complete failure” of Fit to Discharge proceedings before Lieven J: Carers suspended, allegations of abuse, and no immediate prospect of discharge

By Celia Kitzinger, 30th August 2026

An already appalling situation has become even worse for the vulnerable woman in these long-running Court of Protection proceedings. The judge, Mrs Justice Lieven, described the recent turn of events as “extraordinary”.

In brief, the court determined about a month ago (on 28th July 2026) that it was in the best interests of the protected party (“P”) to be discharged home from hospital as soon as practicable, with care provided by “The G Agency”. Since then, allegations of abuse have been made against this agency’s carers by both the Official Solicitor and by family members. A safeguarding investigation is underway with Essex County Council. The G Agency has suspended six members of its staff, and the local authority has terminated its contract with them. The woman at the centre of the case remains in hospital and the ward now has an outbreak of CPE[1], an antibiotic-resistant ‘superbug’ , and P has tested positive. The hospital plan is to temporarily close the ward in order to deep-clean it, but (as of 21st August 2026, the date of the last hearing) there was nowhere for P to go. And as long as P remains on the ward, more than 30 beds remain unavailable, creating what the Trust calls “an extremely unsafe position” for other patients.

These are the latest developments in a case (COP 13630253) concerning a vulnerable woman who’s been in hospital and deprived of her liberty (despite being fit for discharge) for more than a year. The delayed discharge was initially caused by extensive delays in completing a care plan and has since been compounded by her home having been left dirty and unsafe by carers – and now by the allegations of abuse. All the parties agree that staying in hospital is not in P’s best interests.  She has a moderate learning disability, complex post-traumatic stress disorder, generalised anxiety, dissociative disorder, epilepsy and has recently been diagnosed with “Autism Spectrum Disorder”. The situation she’s now in has been described as “counter-therapeutic“: it’s contributing to her distress, dysregulation and “significantly challenging behaviours”. But there’s still no realistic plan for getting her home.

We’ve described earlier hearings in this case, starting in September 2025 when it was before HHJ Hilder)[2]. Over the course of more than 14 hearings, first before HHJ Hilder and then before Mrs Justice Lieven, these experienced and hands-on judges have failed to achieve what all parties agree should happen: P’s safe return home. It seems that even repeated robust judicial intervention cannot make a dysfunctional system provide the necessary care.

The allegations against The G Agency, which has been providing care for P in hospital, are serious.  Evidence includes video footage said to show P being pulled or dragged through a doorway by her ankles while saying “ow”, photographs of P’s unexplained bruises, CCTV coverage of an incident of restraint (also witnessed in person by P’s legal representative), and more. The Official Solicitor, acting for P, has expressed “immense concern that … despite the many legal teams involved in these proceedings, and the oversight of the court, [P] has been subjected to wholly inappropriate care and sustained multiple injuries”. 

The plan was for this same care agency to support P after her discharge home. That’s now, obviously, off the table – yet without an alternative care package P cannot leave hospital. As Lieven J put it in the course of the most recent hearing: “P is continuing to receive what we consider to be abusive care – and the court is in the extraordinary position of authorising that as being in her best interests because there is nothing else available”.

This case exposes the limits of the Court of Protection’s powers when the problem is not disagreement about what should happen, but the apparent absence of a safe and workable way to make it happen. More than a year after P became fit for discharge, and despite repeated judicial intervention, she remains in hospital where she has been exposed to inappropriate and ”abusive” care.

This blog will:

(1) Recap on the delays in getting P home earlier in the proceedings, before the July 2026 hearing: first, the failure to comply with court orders to produce an eating and drinking plan; then the “terrible state” of P’s home; and finally concerns about unsuitable and possibly abusive care.

(2) Summarise key events between the hearings of July and August 2026, leading up to The G Agency’s contract being cancelled the evening before the August 2026 hearing.

(3) Describe what happened at the August 2026 hearing.

I’ll end with (4) Reflections.

1. Delays in getting P home before the July 2026 hearing

The most extensive delays in returning P home  (delays amounting to more than 10 months) arose from the ICB’s repeated failures to provide a care plan covering how P’s eating and drinking would be managed at home. Further delays in the last couple of months were occasioned by P’s home not being in a fit state for her to live in, and most recently by concerns about the quality of care provided by The G Agency – an agency which was appointed on 13th July 2026 after a previous agency had unexpectedly served notice.

Eating and drinking plan: The ICB and LA were initially directed to file a care plan by 29th July 2025, to include how P’s nutrition and hydration needs would be met on return home. They did not comply – and this was followed by (at least) three more court orders with successive deadlines (1st December 2025, 27th May 2026, and 15th June 2026) before the care plan was finally produced. Reflecting on the public bodies’ repeated failure to comply with court orders, Lieven J said (at the hearing on 5th June 2026) “I apologise to (P’s siblings), who must think that the justice system is a bit of a joke. But we have to do our best”. There is now a plan in place, plus clinicians have recently said she can go home with the NG tube in place, which makes things more straightforward. It is entirely opaque to me why a care plan the judge ordered to be produced by 29th July 2025 was delayed for such a long time.

By the hearing of 29th June 2026, a plan was in place for P to go home in the week beginning 27th July 2026. But given the history of the case, the judge was clearly sceptical about the likelihood of this happening without judicial “micromanagement” (her term).  She referred to “a distinct feeling that the moment I’m off the job things might not happen” and wanted to know the “granular detail” of the proposed arrangements to check that the parties were not merely saying they agreed “for the sake of the hearing” before “reneging later”. A timetable was agreed, and a further hearing listed for 28th July 2026, with the expectation that P would be discharged home on 30th or 31st July 2026. “For the next four weeks”, said the judge, “everyone’s focus should be on getting P out of hospital”.

At the hearing on 28th July 2026, at the beginning of the week when P’s discharge home should (finally) have taken place, everything began to unravel, with two key concerns: the state of P’s home and the quality of care. 

The state of P’s home: Given the indication that P might be going home soon, P’s siblings had gone to her bungalow (purchased for P with NHS England funding) the day after the 29th June hearing and they reported that it was in a “terrible state” and not fit for her to return to. Problems included: dishes with mould in the dishwasher, swarms of dead bugs everywhere, filthy floors, out-of-date food in the cupboards, broken office furniture abandoned by a previous care agency, none of the hoists and slings had been serviced, the sensory room needed maintenance, and the broken footrest on the wheely recliner chair needed to be repaired. Bags from McDonalds and cups from Starbucks had been left all over the office room (used by staff – none of this was P’s) rather than binned and disposed of, and the office carpet was heavily marked. Agency staff (they said) had “shown a real lack of respect to [P]’s home and her possessions”.  The two siblings had started tidying up but it was beyond what they could reasonably be expected to achieve without professional help.

Concerns about carers:  P is being provided with additional care and support in hospital by a care agency (“The G Agency”) commissioned by the Trust responsible for the operation of the hospital in which P is cared for[3], as the hospital staff were not considered able to meet P’s needs.  There had been two previous care agencies in this role, both of which had given notice. By this point there were also serious concerns from the Official Solicitor and from P’s siblings about the standard of care provided by The G Agency. They’d been caring for P in hospital since 13th July, and the plan was that they would care for her at home.  P had told her legal representative (from Irwin Mitchell) that she did not want to go home with The G Agency’s staff: she did not feel safe with them, and she used the words “abuser” and “attacker”.  It was reported that The G Agency carers had not learned Makaton (as directed by the court), so could not communicate with P,  which was a known ‘trigger’ for her to become dysregulated – which in turn meant that she was then restrained.  Carers were also using known triggers such as saying that P “has capacity”, that the police will be called, and hat she has injured staff.  According to the siblings: “P currently has a staff team that cannot communicate with her and who are restraining her physically and chemically frequently. They do not appear to be taking a trauma informed approach, or understand that a trauma informed approach is needed. P is calling [her sister] 50 to 100 times a day to say she is unhappy/scared” and that she “does not want to go back to the bungalow with The G Agency‘”.

An incident of allegedly inappropriate restraint had been witnessed by P’s legal representative (from Irwin Mitchell) when she visited her client on 20th July 2026. During a conversation about returning home with The G Agency, P became upset. She lowered herself from the bed onto the floor, and was shouting, but not self-harming or causing a risk to anyone else. Three carers entered the room and, without asking the legal representative what was happening, they physically restrained P. There were no attempts at de-escalation and no other options for managing the situation were discussed or considered. According to the OS, “There was no immediate risk of harm that warranted three people holding her down. It was the intervention by staff that caused her to become agitated and to hit out“.

On the evidence currently available, the Official Solicitor considers that on 20th July 2026, “known triggers were not avoided; de-escalation strategies were not followed; there was no immediate risk of harm to [P]; physical restraint was not used as a last resort and was not proportionate. A safeguarding referral has been made by Irwin Mitchell to the relevant safeguarding body, which is Essex County Council”. The OS also notes that the care record provided for 20th July “contains no reference to the use of physical restraint at all which is extremely concerning” and a violation of the Health and Social Care Act 2008 (Regulated Activities) Regulations 2014, regulation 17, which is enforced by the Care Quality Commission.

The incident of 20th July had been recorded on CCTV. On 22nd July, P’s sister noted new bruises and a new graze on P’s chest which was bleeding.  These concerns superseded the agenda for the Round Table Meeting, convened on 22nd July 2026 to discuss final steps for getting P home.  Professionals from the ICB and LA then reviewed 3 hours of CCTV footage covering the visit on 20th July 2026, along with the attendance note, the daily care records and statements from a carer and a nurse employed by The G Agency who were involved in the use of restraint. They took the position that, on balance, the degree of restraint used was proportionate (though the LA’s legal representatives had not had the opportunity to review it yet).  They noted that the final and independent determination of whether P has been subject to abuse will rest with the safeguarding authority, Essex County Council. In the meantime, they suggested the need for “a communication protocol so that any family concerns about the care being delivered can be sent to senior managers, as opposed to being raised with individual carers directly”.

At the 28th July 2026 hearing, all this was reported to the judge.  P’s siblings described the new care providers as “the worst agency they’ve been involved with” and said that P was begging them to stop her having to go home with them.  The Official Solicitor said she was “gravely concerned following that visit that [The G Agency staff] are unable to meet P’s needs and provide appropriate care to her, and that their use of physical restraint on [P] on [20th July 2026] was unlawful”. She was not optimistic that P would return home as planned but was “at a loss” to suggest how best to proceed: “After at least 14 court hearings, many more orders having been made on the papers, multiple expert reports obtained and a costs order made on the Official Solicitor’s application against two of the statutory bodies, the Official Solicitor is somewhat at a loss as to what else can be done to get [P] home with an appropriate package of support”.

Although, at the July hearing the judge was sympathetic to concerns from both the Official Solicitor and the siblings about the care company, she wanted no more delay: “They are the only carers prepared to work with P …  if we start looking for new carers, we’ll be back to square one”. The judge (described by one observer as “furious”) demanded “a remorseless focus on getting P out of hospital” and authorised care and restrictions to continue with The G Agency. 

At the hearing a month later, when the care package had irretrievably broken down, the OS was to say, grimly, to the judge: “It gives me no pleasure to say ‘I told you so’”.

2. Between the hearings of 28th July and 21st August 2026

Events moved quickly over the (almost) four weeks between these two hearings.  I have pieced together what happened from what is recorded in the parties’ position statements for the 21st August 2026 hearing.

2.1 A judicial meeting (5th August 2026) followed by an application for the judge to recuse herself.

In a very unusual move for a judge in this situation, Lieven J pursued an earlier proposal to chair a meeting outside of court to resolve concerns about the care package. This meeting took place on 5th August 2026 and resulted in a plan to discharge P to her bungalow on 14th September 2026, with care provided by The G Agency.

Discussions also took place about the possibility of appointing a “Super Care Coordinator” (a named consultant clinical psychologist) who would be responsible for overviewing and managing the situation going forward. The view of the Official Solicitor was that this is essential since “it has been conclusively demonstrated in the course of these proceedings that the existing MDT [Multi Disciplinary Team] are not capable of getting [P] home with a sustainable care package in place”.

The proposal for a “Super Care Coordinator” was opposed by the public bodies, who consider that they “can and should continue to work collaboratively to manage P’s case moving forward”. According to the local authority, “adding another layer of management is unnecessary and may cause further delay”. It’s not within the powers of the judge to order this appointment.

After this meeting (and a subsequent Round Table Meeting), the local authority submitted an application that Lieven J should recuse herself, arguing that the judicial meeting was analogous to a Financial Dispute Resolution appointment in family proceedings or a dispute resolution hearing under the Property and Affairs Pathway, so that it was not appropriate for her to continue to act as a judge in the case. They also claimed that some of what Lieven J said in that meeting indicated “bias” and that the judge had “formed a concluded view on the central issues in dispute”.  One example (it’s taken from notes made during the meeting and quoted by the siblings who opposed the recusal application) is this series of questions from the judge:

“How is [The G Agency] going to check implementation of training and check it’s being absorbed. You don’t grab ankles of someone who has autism and no sense from the video of people who are autism and trauma informed. What are [The G Agency] going to do to make sure training is absorbed and implemented. […] Everyone who watched that video would say things went wrong – mistakes happen but learn from them. [In terms of training] “one of the most useful things is to watch the video and if you watch it, there are some obvious lessons.”

The siblings submitted that “these comments do no more than express concern about one interaction caught on video and show the judge asking for information about training and communication in order to facilitate a discharge with The G Care Agency”. 

In the event, the application for the judge to recuse herself was withdrawn before the next hearing (I don’t know why, but I assume because the agency in relation to which the judge had allegedly displayed bias was now out of the picture).

2.2 Decision made to temporarily close ward due to ‘superbug’ (10th August 2026)

A ‘super-bug’ outbreak (Carbapenemase-Producing Enterobacterales (CPE)) on the ward means that all patients (except P) are in the process of being discharged so that a full deep clean can be done. P has tested positive for CPE (although she’s asymptomatic) but this means she cannot be transferred to another ward due to the risk of spreading the infection to other parts of the hospital. According to the ICB and Trust, closure of the ward means that more than 30 beds cannot be used and the Trust responsible for the operation of the hospital says this will have a significant impact on patients and presents operational difficulties for them and for the local ambulance service: “if the ward is not able to reopen for an extended period of time whilst discharge planning for [P] continues, this will leave the Trust in an extremely unsafe position”.

2.3 Round Table Meeting (17th August 2026) and a second incident of alleged abuse

At the Round Table Meeting held on 17th August 2026, there were further concerns about what the Official Solicitor and P’s siblings considered could constitute “abusive” treatment of P from the carers. Nonetheless (according to the OS), “none of the statutory bodies were concerned that there was an immediate threat to [P’s] welfare“.

The video of the “ankle-pulling” incident from the previous Friday did not become available to the parties until after this meeting and there was a discrepancy in reports about what had happened. It was said on behalf of The G Agency that carers were only holding P’s legs down, not pulling or moving her.

The video was shared the following day, and the OS says that it “shows [P] being pulled by the ankles through a doorway while the carer pulling her says ‘come’. [P] calls out ‘ow’ when the pulling starts“. The carers’ notes that seem to correspond to the video record P’s “very challenging, physically aggressive behaviour towards all staff on duty this morning“, say that she “rolled towards the door” and that she then “took videos whilst she screamed to indicate she was being hurt, later told staff I’ve sent it to tiktok and my Sister During this escalation [P] was held in safe hold to maintain her safety“. There is no indication in the notes that she was being “pulled” or “dragged” by her ankles – but this seems (from what the parties now say) to have been readily apparent from the video-recording.

On the basis of what was said at the meeting, and without seeing this video, the ICB and Trust indicated that in view of the extensive work done to date to provide training and support to the care team and to ensure P’s bungalow was ready, it was appropriate to continue to work towards discharge on 14th September 2026 with The G Agency. They acknowledged the safeguarding concerns raised by the OS and the siblings but took the position that the safeguarding investigation (with Essex County Council) needed to take its course.

This was opposed by both the Official Solicitor and by the siblings.

The day after this Round Table Meeting (18th August 2026), the Official Solicitor filed an application for an urgent hearing to address her serious concerns about P’s welfare. She asked for a different judge (not Lieven J) since “arguments about bias and recusal are an unhelpful distraction which will delay the court focusing on the crucial question of whether [The G Agency] can continue to provide care to [P]“. In a position statement prepared two days later (20th August 2026) for the following day’s hearing, she said she was “appalled that the statutory bodies’ response was to say they needed to see more evidence, take statements from care staff, and let the safeguarding process play out, on the basis there was not enough evidence to suggest that [The G Agency staff] should not be providing care to [P]”.

The Official Solicitor’s position was that The G Agency “are providing care to [P] which is not safe, is not in accordance with court-authorised care plans, is not in her best interests, and which infringes her rights under Articles 3 and 8 ECHR”.  Accepting that P does exhibit challenging behaviour and that caring for her is not easy, the OS points out that, despite this, “previous care agencies have been able to provide care that did not result in her sustaining bruising injuries and being physically restrained in this manner“. The OS also points to multiple other deficiencies with The G Agency that have arisen in the context of trying to improve the care they provide. These include: failure to provide details of their proposed training, no plan for staff reflection and learning, and no Positive Behaviour Support (PBS) plan designed to avoid situations where restraint or other physical intervention may be required, and to support the use of de-escalation strategies where avoidance has not been successful, and ensure the safe use of restraint. The OS also expresses her concern that although the ICB say that they review the care provided to P, this review appears to depend on The G Agency sending them accurate records “which as has been demonstrated by the disclosure in these proceedings, is not happening“.

The siblings refer to manifold failings of the carers (manual handling which is not in line with any care plan and which has injured their sister; over reliance on restraint, both physical and chemical; failure to engage positively with her; using known triggers; and failing to learn Makaton): they had “lost all faith that the G care agency might change their approach“. Their view was that sending P home with The G Agency would “set P up to fail so that readmission to hospital is inevitable, leading to further deterioration and institutionalisation”.

2.4 The G Agency’s contract is terminated (evening of 20th August 2026)

The G Agency informed the ICB (on 20th August 2026) of their decision to suspend 6 members of staff. In the light of this, and on the basis of their own review of CCTV footage, the ICB decided to terminate their contract with the company and served notice that evening (Thursday 20th August 2026).

The ICB then brought in the Chief Nurse and Head of Safeguarding to provide oversight and input to the care team, and said they were continuing to “actively monitor and respond to the situation as it evolves”.  They were liaising with the LA urgently to consider alternative care arrangements: it was possible that the previous care agency might step into bridge the gap (albeit only while P remains in hospital). They also said that spot checks would be made overnight by ward staff, some of whom are already trained to work with P and others of whom would  be shown a training video to help them. They now (finally) recognised that the allegations (and evidence) of abuse meant that the planned move of 14th September 2026 could no longer take place. They were urgently seeking an alternative home care provider.

2.5 Progress on making P’s home safe and habitable

More positively, P’s bungalow has been professionally deep-cleaned and repairs have been carried out. The plan is to install CCTV in early October. There’s some dispute about the use of body-worn cameras in the meantime, and also subsequently in areas not covered by CCTV (e.g. the bathroom) but it wasn’t suggested that this would delay P’s move.

3. Hearing of 21st August 2026

This was a remote hearing that lasted 35 minutes, with the following parties:

  • NHS Norfolk and Suffolk Integrated Care Board and Essex Partnership University NHS Foundation Trust (as joint applicants) (ICB and Trust) represented by Claire Watson, Serjeants’ Inn Chambers. (The ICB and local authority are jointly responsible for commissioning P’s s.117 MHA 1983 aftercare package.)
  • P’s siblings represented by Anna Bicarregui, 39 Essex Chambers (acting pro bono)
  • Suffolk County Council (the local authority) represented by Sophy Miles, Doughty Street Chambers
  • The protected party (P) by her litigation friend the Official Solicitor (OS) represented by Victoria Butler-Cole KC, 39 Essex Chambers
  • Hertfordshire Partnership NHS Foundation Trust (HPFT) – acts as P’s care coordinator and is  responsible for community learning disability services in the locality of P’s home but are “not responsible for commissioning any part of P’s package of care and support, nor for the monitoring of its quality”

The judge had slotted in this hearing as an urgent matter while she was on vacation, beause at the last hearing she’d anticipated being able to authorise P’s return home.  Obviously, that wasn’t now going to be possible since the contract with The G Agency had been terminated the evening before and no alternative care team had yet been sourced. 

The judge opened the hearing by saying: “The reason for urgency of this hearing was to get P home in a couple of weeks time. That’s not going to happen because we’ve got to find a new care provider. So, I’m not really sure what there is for me to decide today”. She also noted that the application for her to recuse herself had been withdrawn, so that wasn’t something she needed to deal with.

The judge then addressed the application from the Official Solicitor for appointment of a “Super Care Coordinator” – the named consultant clinical psychologist – and for his team to step in to support a different care agency as an urgent interim measure. She said: “I appreciate there’s an argument about whether another person should be appointed to coordinate care. I’m not convinced that’s a matter I can- (she breaks off and restarts) I think that’s an NHS internal matter.  It is, to put it mildly, disappointing, Ms Watson [counsel for the ICB] that the care coordinator hasn’t engaged with P and that P won’t engage with the mental health nurse”.  (Later in the hearing the judge said: “of twenty-four people paid by the public purse, only one of them had met P”, adding “it shocks me beyond belief”.)

The Official Solicitor explained why the proposal to appoint a “Super Care Coordinator” was important:

OS: There is more than enough evidence that carrying on as we are is not working. It’s been a complete failure.

Judge: No, that there is a complete failure is clear. I think that’s right as a matter of law. So, is there anything for me, in my appropriate jurisdiction, to do today?

OS: It gives me no pleasure to say ‘I told you so’ at this hearing.

Judge: No, no, hands up!  It’s extraordinary we’re still in this position. P is continuing to receive what we consider to be abusive care – and the court is in the extraordinary position of authorising that as being in her best interests because there is nothing else available. And now P has- the entire ward has an infection. There’s nothing I can do about that. If I were the hospital, I would start possession proceedings. The hospital has been extraordinarily compliant […]. I think this case is moving out of the COP and into the administrative court.

There was some discussion with counsel for the ICB about whether P should be moved to a mental health unit as an interim measure. The judge was clear that she doesn’t think it’s in P’s best interests to be detained under the Mental Health Act and placed in a psychiatric hospital but she did entertain the possibility that “carers attuned to Ps needs might be a better option than [The G Agency staff]”.  Counsel for P’s siblings conveyed their strong opposition to that possibility, and the judge replied: “I urge your clients not to turn your faces against it completely. She will have to move out of where she is right now because of the infection. I urge them not to turn against it irrevocably before they’ve even gone to have a look”. This is an indication of how bad things have become at the hospital, since at a previous hearing Lieven J had said that a psychiatric admission would be “very counter therapeutic”, and that she feared that if P were to be admitted to a psychiatric hospital, “it may be a very long time till we can get her out again”.[4] It’s a significant turn-around that she’s now asking the siblings to give serious consideration to a psychiatric admission.

When the judge asked whether there was “any point in listing a hearing for the second half of September”, when she’s back from holiday, the OS thought that would be useful so as to get “something from statutory bodies as to what their medium-term proposal is. By then there will have to have been some proposal made about who is going to look after P and what’s going to happen”.

The next hearing is to be listed before Mrs Justice Lieven at 3.30pm on 15th September 2026, for one hour – and the judge proposes also to deal with a costs application from the OS if there is one at that hearing. Given the relatively short timescale, the September hearing is very unlikely to be the final hearing in this case – so, as Mrs Justice Lieven has recently been appointed as a new Court of Appeal judge, the final determination of where P goes next and the arrangements for her care will rest with a different judge, possibly (her name was mentioned in the hearing) the COP Vice President, Mrs Justice Theis.

The judge ended the hearing by saying: “I hope things get better. I struggle to see them getting worse at the moment”.

4. Reflections

It’s been a sobering experience to follow this case and to witness the dismaying series of delays, and now the alleged abuse, affecting a vulnerable woman.  This sequence of events occurred despite devoted and highly efficient siblings advocating on her behalf, despite agreement between the parties that she should be discharged from hospital, and despite the efforts of two very experienced senior judges over the course of almost a year. It’s self-evidently a systems failure of spectacular proportions. I wish I could say it was “unbelievable” or a “one off”, but most of us with relatives enmeshed in the health and social care system find it only too familiar.[5]

The most shocking aspect of what has happened is (for me) the decision by the judge to continue to authorise The G Agency to care for P following the hearing of 28th July 2026, at which point, on the basis of the Position Statements I’ve seen from that hearing, there were sufficient “red flags” indicating that the care was (at best) inadequate and that P should not be discharged home with those carers in place. Of course, it is easier to see this with the benefit of hindsight, given the additional evidence of harm to P from The G Agency carers after 28th July 2026.  I do understand the judge’s “remorseless focus” on the need to get P out of hospital promptly (which required an admittedly inadequate care team to remain in place), especially with the possibility of detention under the Mental Health Act in prospect, as P became increasingly dysregulated in hospital[6]. But by the hearing of 28th July 2026, and again at the time of the judicial meeting on 5th August 2026, the serious problems with The G Agency were very apparent, and it’s not surprising that Lieven J’s hope that they could be fixed by further training failed to materialise.  Instead, the court left P exposed to potential further abuse. As a result, by the hearing of 21st August 2026, the judge seemed to be advocating detention under the Mental Health Act as possibly the least worst option for P, despite have previously expressed concern that this would be “very counter therapeutic” [7]

As the Official Solicitor points out, there have been a multitude of reports and investigations raising concerns that reflect what seems to have happened here: undignified and inhumane care; treating people not as individuals but as a collection of negative behaviours; not listening to disabled people and their families when they raise concerns; and not acting promptly when red flags are raised.[8]  On this occasion, these systemic failures occurred while P’s welfare was actively being overseen by Mrs Justice Lieven – on her watch.

Finally, some reflections on ‘deprivation of liberty’ in this case.

At the hearing on 29th June 2026, the court determined on an interim basis that P is deprived of her liberty by virtue of her care arrangements in hospital, and authorised this pursuant to s.16(2) and s.4A(3) MCA 2005.  At the hearing, in response to the application from the ICB and Trust, Lieven J said she was “not going to make a ruling on the applicability or otherwise of the Supreme Court judgment to the facts of this case”.  Instead, given the situation at that  point, which included the risk of P’s detention under the Mental Health Act, she considered it “necessary and proportionate” for P to be deprived of her liberty in hospital on an interim basis. She added: “I’m not going any further than that”. This DOLS authorisation expired on 21st August 2026 and I think (though I haven’t seen it recorded anywhere) that Lieven J must have approved its renewal.[9]

The judge had earlier stated (in the course of a hearing) that she hoped, once a care and discharge plan had been approved, to make a determination as to whether or not the conditions of P’s care and residence in the community were such as to constitute ‘deprivation of liberty’, and she commented: “It would be a perfect case for me to say it’s just not a deprivation of liberty given the decision of the Supreme Court” [i.e. in AGNI,].  The judge’s position on ‘deprivation of liberty’ is well known since she has  famously taken an approach to deprivation of liberty (in [2024] EWHC 1690 (Fam)) that was not consistent with the Article 5 framework established in Cheshire West and her judgment on that matter was successfully appealed. In the (unlikely) event that new carers are in place so that P can be discharged home at the next hearing before Lieven J on 15th September 2026, it seems very likely that she will find (in line with AGNI) that there is no ’deprivation of liberty’ for P (despite the CCTV, restraint etc).

The ICB takes a different view: “In the event the court determines that it remains in [P]’s  best interests to be discharged back home, the ICB considers that [P] is likely to be deprived of her liberty that will require the authorisation of the court under the MCA 2005, particularly given the level of restrictions in place, the continuous nature of supervision and the likelihood that she will raise objections to the care being delivered.”

The Official Solicitor “has not formed a concluded view as to whether P’s care at home engages Article 5” but does note that a care plan permitting three or four staff to restrain P on the floor, and the use of sedating medication, “may be closer to the paradigmatic police cell … than would ordinarily be the case with a package of care in a person’s own home”.  Like many advocates for P post-AGNI, she turned from Article 5 to Article 8 and is: “quite sure that [P’]s Article 8 rights are engaged by the plans for her support, and the method of their implementation”. She “does not consider that the point has been reached when this court could sign off on her care arrangements as being in her best interests and conclude the proceedings”.

That last point, at least, is surely indisputable.

Celia Kitzinger is co-director of the Open Justice Court of Protection Project. She is on LinkedIn (here), and also on X (@KitzingerCelia) and Bluesky (@kitzingercelia.bsky.social)

END NOTES

[1] “CPE” stands for Carbapenemase-Producing Enterobacterales – a ‘superbug’ identified as an increasing threat to public health internationally. There’s more information about the challenges associated with outbreaks of CPE in this (open access) scoping review: Healthcare workers’ experiences of caring for patients colonized with carbapenemase-producing Enterobacterales (CPE) in an acute hospital setting – a scoping review. Recent outbreaks in England are referenced in (for example) a description of the control measures in place in a cardiothoracic unit at the Royal Papworth Hospital in Cambridgeshire in June 2024 and a report from the Chief Medical Officer (2025) of an outbreak at a hospital in Greater Manchester.

[2] There are blog contributions about earlier hearings in this case from five different public observers (Kim Dodd, Amanda Hill, Elissa Novak, Sandra Preston, and Tim Sugden) as listed below. I’ve drawn on them (and in some cases the observers’ notes) in summarising events prior to the hearing of 21st August 2026.  I am also grateful to the judge for ordering disclosure of the parties’ position statements (opposed, as usual, by the Official Solicitor) for the hearings of 28th July 2026 and 21st August 2026 which have greatly assisted with transparency. I requested the “Gardner documents” as an alternative (or addition) but they weren’t mentioned in court and I suspect they had not been prepared. The judge heard submissions and, in the particular circumstances of the case, considered disclosure of the position statements to be necessary for observers to understand the proceedings.  Redactions were considered and not approved by the judge. Where I’ve used quotations from what was said in the hearings, these are based on contemporaneous notes (mine, or other observers’) and are as accurate as we could make them but are unlikely to be absolutely verbatim. Here’s a list of our previous blog posts about this case.

[3] The name of the hospital is protected by the Transparency Order (because it’s where P currently resides and receives care) so I’ve avoided naming the Trust. They are not a party, although they have been involved in ongoing Round Table Meetings and a representative has attended court hearings.

[4] As quoted in a blog post about the hearing on 29th June 2026 The ‘fit for discharge’ story continues: 10 months on 

[5] See Reducing restrictions for a person deprived of his liberty: internet use, access to services and ensuring appropriate support  in which Jenny Kitzinger says: “After my own sister, Polly Kitzinger, was brain injured in a car crash, I quickly realised that there were not just barriers to service provision, but also a maze of false promises, false starts and delays. As a family, we certainly learned about the need for persistence and attention to detail if Polly’s needs were to be met …” The case reported in Jenny’s blog was heard by HHJ Hilder, who also dealt with earlier proceedings in the ‘Fit to Discharge’ case reported in this blog post. Like Lieven J, she strives to achieve the best for protected parties and is aware of the “micro-management” (Lieven’s term) that is often required. The blog comments on HHJ’s “knowledge of how a person might fall between the gaps of service provision, her obvious awareness about how delays can occur, and her sheer attention to detail to ensure her order would be as effective as possible“. This approach is characteristic of both HHJ Hilder and Lieven J which make it doubly alarming that these two judges have been defeated in their efforts to ensure P’s undisputed best interests (discharge home) for over a year.

[6] The latest data recorded 2,130 people with a learning disability and autistic people in inpatient services.  Of these, 1,030 (49%) had been there for more than two years, and 320 for more than ten years. In 2023, an investigation by The Independent revealed that 27-year-old Nicholas Thornton had been trapped in inappropriate settings, including psychiatric hospitals, for a decade, because NHS and social care services were unable to fund a place that could meet his needs in the community. Mr Thornton was finally granted a full community care package in 2024 and his own home, following the exposé. (“Fears patients with learning disabilities ‘will remain trapped in hospitals’ despite Mental Health Act changes”, The Independent, 19th December 2025)

[7] As quoted in a blog post about the hearing on 29th June 2026: The ‘fit for discharge’ story continues: 10 months on 

[8] Out of sight – who cares (CQC, 2020); Baroness Hollins’ report My Heart Breaks 2023; Transforming Care: A national response to Winterbourne View hospital (DHSC 2013)

[9] The potential value to P of having the protection of DOLS in hospital is illustrated by the Official Solicitor’s observation that deprivation of liberty in hospital “requires that [P] is provided with ‘a suitable medical environment accompanied by real therapeutic measures with a view to preparing them for eventual release’, Rooman v Belgium [2020] MHLR 250”.  She observes that there is still no proposal for P to receive individual therapy while she is deprived of her liberty in hospital and that the care being provided by The G Agency is “counter-therapeutic”.

Reducing restrictions for a person deprived of his liberty: internet use, access to services and ensuring appropriate support

By Jenny Kitzinger, 26th August 2026

Since the AGNI judgment I’ve closely followed developments around deprivation of liberty and I’ve written about what changes in the meaning of “deprivation of liberty” might mean for my brain injured sister, Polly. So, when I found myself near London and with an unexpected free morning, I was pleased to discover that the lists showed two Court of Protection hearings about deprivation of liberty at First Avenue House, the London headquarters for the court. Both hearings were listed as public, and both were for one hour before Senior Judge Hilder.

This blog is about the 11.30 am hearing on 17th August 2026 (COP 20015410).

Transparency

I turned up at First Avenue House with no notice at all (because I was not sure I trusted my train to get me there on time), but a member of the court staff was very welcoming, provided printed copies of the Transparency Orders for both hearings, and showed me to the waiting room. He also kept me informed about when the hearings would start (both a little late) which meant I could then catch my breath. Knowing I was now in the right place and on time to attend, I also emailed requesting the ‘Gardner documents’[1] or position statements, to back up my verbal requests at the desk.

Once in court, HHJ Hilde asked if I’d received the Transparency Order and whether I wanted any other information and then asked the barristers about the availability of the relevant documents – none of which were easily produceable for me, so the judge simply provided a succinct verbal summary, which was invaluable in allowing me to follow proceedings.

Overall, this was also a very positive experience for me as an observer. Although some judges can treat our presence as disruptive or time-consuming, Senior Judge Hilder made it all seem easy to accommodate me in court. She is an exceptionally clear communicator, and her clerk is welcoming and well versed in the principles and practice of transparency.

Background to the case

The protected party [P] in this case is a 25-year-old man with ADHD, mild intellectual impairment and autism.

He currently resides in a supported living placement (with one other resident, and a care team). He has 10 hours of one-to-one supervision during the day as well as waking night supervision. There are locked doors and windows, CTV motion censors in communal areas, and a perimeter fence. In addition, due to having committed a criminal offence, he is under probation restrictions which mean he cannot go out by himself.

P also has no access to internet on his phone: it is not a ‘smart phone’, and is only really functional for calls and texts. He is supervised when accessing the internet using a device other than a phone.

The hearing was focussed on his residence and care arrangements – and specifically, on trying to progress determination of capacity and decide what restrictions should be continued and where a trial of reduction in some restrictions might be in his best interests, if he could be provided with specialist support.

He was represented, via the Official Solicitor, by Victoria Butler-Cole KC who joined online.

One of his mothers (they’d adopted him when he was a toddler) was present in court. I think she was a litigant in person.

The London Borough of Haringey was represented by Joanna Thom  

The hearing

The barrister for the Local Authority (the London Borough of Haringey) informed the judge that the expert report prepared for the court found that P lacks capacity in relation to decisions about legal proceedings, care, and use of social media, but that he does have capacity to engage in sexual relations.

His mother clarified that she agreed he had capacity to engage in sex but believed he needed support around knowing the age of his sexual partner and knowing “how you have a relationship”.

Pre-discussions between all parties had resulted in an agreed draft order placed before the judge which explicitly stated that he has capacity for sexual relations but lacks capacity to make decisions “about with whom he should have contact”[2]

All parties seemed to agree that the main restrictions are in his best interests, at least for the moment, with the exception that there was discussion about how to increase his access to the internet.

The judge had spoken with him that morning (a “polite and delightful young man”) and, despite the objective restrictions on him, he’d told her that his experience of where he was living now was going “brilliantly”. It is “homely” and he feels warm and safe there, and he accepts the restrictions.

He had, however, told her he was very unhappy about having a what he called a “brick phone” without internet access: – “he didn’t even want to show it to me as he is embarrassed by it”.

He can’t make video calls or use it to organise football or cinema tickets or order take aways, nor – he’d explained – could he use it to address problems with his universal credit. The judge said she’d talked to him about ‘Cyber Spider’, a safeguarding service supporting safe internet use, and he was in principle okay with having the Cyber Spider App put on a phone with internet access.  She added: “I said his phone wouldn’t change overnight, but we would try to sort it”.

It soon became clear that when Senior Judge Hilder says she will try to get something sorted she is determined to do so, and leaves little room for error or delay. A significant part of this hearing was used to ensure that initial efforts to reduce P’s restrictions in this area would be followed through and that the order was written in a way that would support this to happen quickly.

Ms Thom for the Local Authority (the London Borough of Haringey) said that the Local Authority had agreed to commission Cyber Spider, and was simply awaiting confirmation of the time frame. Some judges might have left it there. Not Senior Judge Hilder. The conversation then went like this:

Judge: Be more specific please in the order about when Cyber Spider will be available

Ms Thom [Local Authority]: The request had been made.

Judge: Has it been sent to Cyber Spider?

Ms Thom [Local Authority]: There’s been an agreement they’ll be commissioned, but the invoice needs to be paid in advance.

Judge: Specify in the order a date by which that invoice will be paid.

It was agreed to specify (by way of recital) the date of 21st August 2026. The judge then asked when a Cyber Spider assessor would talk to P and how long the assessment would take. Once she had this information she wanted at date of 28th August 2026 as the assessment deadline and then turned to questions about getting P’s phone back, so the software could be installed on it.

Judge: The hardware – how will we get that?

Ms Thom [Local Authority]: His phone is currently held by the police.

Judge: How will the handset be made available. My understanding is that the police haven’t released the phone to [P], and won’t release it to either of his mothers. So there needs to be an order which allows that phone to be released.

The judge then went on to check who would give the order to the police and collect the handset (the mother said she would) and whether there was a named police liaison officer (there was). The judge suggest that the Local Authority send the order in advance to the named officer (as well as his mother taking in the paperwork), so that the police would then be ready to hand over the phone. 

Once she had checked the timetable and step-by-step process Senior Judge Hilder concluded by saying that the order should include the statement that the court was expecting the phone to be available to him, with the Cyber Spider App on it, by the 4th September 2026.

The rest of the hearing was devoted to trying to ensure appropriate support services. It was clear this had so far not been provided. Ms Butler-Cole commented that: “Currently his placement is not far short of prison if no support is being provided to reduce restrictions.”

It seemed that the Trust (North London NHS foundation Trust) had not provided support via the community ‘single point of access” mental team nor via the learning disability team – apparently partly on the grounds that this young man doesn’t have a learning disability. “But in Dr X’s report that diagnosis IS given – so we can start with that team” said Ms Butler-Cole. The Local Authority was going to send the medical report to the Trust. The judge asked for the name of the person in the Trust who would receive the report, and added “By the time the order is submitted I’d like that specified”. 

The Official Solicitor was clearly very concerned about what had happened.  Their position was that the judge should order the NHS Trust to say if he was not being accepted by either the mental health or the learning disability team and, if so, to explain why not. She requested disclosure of correspondence regarding attempts to get referrals. The judge agreed and stated that disclosure should be of correspondence from 25th April 2025 onwards (the date when these legal proceedings first started). A deadline was set for 4pm on 1st September 2026, by which time the Trust must disclose what referrals they’d received, the outcomes of those referrals, and specify how they proposed access to the support he needs going forward.

If there were to be no acceptable response from the Trust, a hearing would take place on 18th September 2026, with the Trust joined as third respondent, and attendance required at that hearing. Provision was made for vacating the hearing if the Trust gave an acceptable response.

Reflections

The family, Local Authority and OS seemed to be working closely together to try to ensure that restrictions could be reduced, and to ensure that the Trust would provide appropriate support in future.

Obviously, it should not take a court case to resolve such situations, but sometimes it seems to be necessary. Families frequently report having to fight for support for vulnerable children and adults and how difficult it can be to engage the appropriate services. After my own sister, Polly Kitzinger, was brain injured in a car crash, I quickly realised that there were not just barriers to service provision, but also a maze of false promises, false starts and delays. As a family, we certainly learned about the need for persistence and attention to detail if Polly’s needs were to be met and some professionals reacted by describing us as ‘demanding’, ‘obsessive’ or ‘failing to trust’ the collaborative process. I’ve sometimes been seen as confrontational for demanding the name of a responsible individual to contact, for writing ‘too many’ letters as I tried to follow up on failures to act, or, for example, for my eventual insistence that letters were signed for on arrival so there’d be proof they’d been received.

Senior Judge Hilder (and the OS) seemed very familiar with how difficult it can be to ensure that organisations follow through on their responsibility and how easily a timetable can slip. I was interested at one point to hear Senior Judge Hilder apologise to Ms Butler-Cole for being “dictatorial” on a particular point that she was going to put in the order. The very choice of the adjective ‘dictatorial’ reflects Senior Judge Hilder’s authority to, quite literally, dictate the contents of the court order – authority lacking for a sister, even one (like me) who is a court-appointed welfare deputy, trying to advocate for appropriate levels of service provision.

Failing to provide appropriate support to vulnerable people has huge costs for the individual, those around them, wider society and for the very services that are so over-stretched. These costs in some cases include the demands placed on the Court of Protection and (in this case) the litigation costs for the Local Authority and the OS. There should be a more efficient way of dealing with the problems.

Senior Judge Hilder should not have to make detailed orders to ensure that protected parties have access to appropriate services – but I’m glad she does. She was very much on top of the material in this case, and in control of her court room. I admire her obvious commitment to understanding and addressing the problems faced by a particular individual, her knowledge of how a person might fall between the gaps of service provision, her obvious awareness about how delays can occur, and her sheer attention to detail to ensure her order would be as effective as possible.

I do hope the Trust gives an acceptable response to SJ Hilder’s order and that services are now put in place. I hope that the hearing on the 18th September 2026 can be vacated – but I won’t hold my breath.

Jenny Kitzinger is co-director of the Coma & Disorders of Consciousness Research Centre and Emeritus Professor at Cardiff University. She has developed an online training course on law and ethics around PDoC. She can be found on LinkedIn here and is on BlueSky as @JennyKitzinger. She is also Health and Welfare Deputy for her sister, Polly Kitzinger.

[1] The ‘Gardner documents’ are (a) the case summary (b) a chronology of relevant events and (c) the issues for determination at the hearing. See: A statement on the Court of Appeal’s judgment in Re Gardner (Deceased) (Court of Protection: Disclosure of Position Statements).

[2] For more on capacity for contact and how this is different from capacity for sex see:  “When capacity for contact and sex do not align: Pragmatic decisions and judicial work-arounds”. https://openjusticecourtofprotection.org/2022/10/24/when-capacity-for-contact-and-sex-do-not-align-pragmatic-decisions-and-judicial-work-arounds/

When compliance is not consent: Applying AGNI when P is sedated and objecting

By Maria Maier, 21st August 2026

What if compliance with care is not the same as consent to it?

And what if the medication a person receives may itself affect their ability to object?

These questions were at the heart of a Court of Protection hearing I observed concerning P, a man living in a care home following a brain injury. The hearing (COP 13665011), before District Judge Clarke, concerned a challenge to standard Deprivation of Liberty Safeguards (DoLS) authorisations.

It gave me the opportunity to see how the Court is approaching the Supreme Court’s new, multifactorial test for deprivation of liberty following A Reference by the Attorney General for Northern Ireland (AGNI).

Observing the hearing

I sent my request to observe the hearing remotely (via MS Teams) at 9:14am and joined the link shortly before 2pm, when the hearing had been listed. At 2:04pm, the court clerk joined the call to let me know that the hearing would be slightly delayed and asked me to read the Transparency Order before the hearing began.

The hearing began at 2:14pm. District Judge Clarke asked me to turn on my camera, introduce myself to the Court and confirm that I had read and understood the Transparency Order.

The Judge explained that she could not provide the case summary, chronology or issues of determination that I had requested (in accordance with PD4B para.4.2(a)-(c) COPR 2017, the “Gardner documents”) because the Court had not received them either.

Counsel then introduced themselves. Ms Love of Garden Court Chambers appeared for P through the Accredited Legal Representative (ALR). I could not see her on the video link and, as there are two Ms Loves at Garden Court Chambers, I could not identify her further. Ms Sophie Casely, also of Garden Court Chambers, appeared for the Royal Borough of Kingston upon Thames, alongside two social workers. P’s wife and one of his two sons were also present.

The Judge then asked Ms Love to provide a brief summary of the case.

Ms Love explained that P had suffered a brain injury following a fall and was now living in a care home, where the Local Authority had authorised standard DoLS authorisations.

The proceedings had been ongoing since 2021 and began as a section 21a challenge to the authorisation of DoLS. P’s wishes and feelings had been considered, and he would prefer to return home to his family. However, all parties agreed that this was not a practical option. The stairs at the property and P’s need for 24-hour care meant that his care needs could not be met at the family home.

Alternative placements had also been considered, but everyone agreed that it was in P’s best interests to remain in his current placement.

DJ Clarke added that at the previous hearing, the Court had identified two main concerns. First, there had been no Mental Capacity Assessment or Best Interests Decision concerning the administration of covert medication. Second, there were concerns about the limited opportunities for P to socialise and engage with the community.

Since then, opportunities for social interaction had improved. District Judge Clarke emphasised that it was ultimately P’s choice whether he wished to engage; the Court would not compel him to do so.

This left one outstanding issue concerning covert medication.

When does covert medication require further scrutiny?

The prescribers had still not provided a mental capacity assessment or best interests decision concerning covert medication. DJ Clarke clarified that there was no criticism of either party for this. The Local Authority did not have the capacity to undertake the assessments, as responsibility lay with the prescribers or GP. However, the GP had communicated either an “unwillingness or inability” to become a party to the proceedings.

The Judge explained that there were several options available to the Court. However, the documents in the bundle stated that covert medication had not been administered for over a year. DJ Clarke continued that if covert medication were being administered on an ongoing basis, she might consider a section 49 report, which requires the NHS or Local Authority to provide expert information, or another hearing with evidence. In the circumstances, however, she questioned whether prolonging the proceedings and pursuing a section 49 report would be proportionate or necessary.

Instead, she suggested that the issue could potentially be resolved through a condition attached to the standard authorisation outlining that covert medication should not be administered without a mental capacity assessment and best interests decision.

Considering AGNI, DJ Clarke further clarified that P would likely be deprived of his liberty. The restrictions imposed upon him were strict, and it appeared unlikely that he was consenting to his arrangements. P had objected to them in the past and, even if he were not currently objecting, a number of his medications had a sedative effect which could affect whether any apparent consent was valid.

The Court adjourned for 15 minutes to allow counsel to consider the position.

When the hearing resumed, counsel for the Local Authority said that they wished to take a “cautious approach”. Ms Casely submitted that there remained some lack of clarity from the GP. Although the clinical lead at the care home had stated that covert medication had not been administered for a year, this had not been independently confirmed by the social workers.

However, Counsel for the Local Authority continued, stating that the evidence suggested that P was compliant with his medication and had not been refusing it. Therefore, they felt that a condition attached to the standard authorisation requiring a capacity assessment and best interests decision before any covert medication was administered would be sufficient. Ms Casely continued that responsibility for the assessments would lie with the managing authority and agreed that the condition proposed by the Judge would be sufficient. There was also a current condition requiring medication to be reviewed every six weeks.

The Judge agreed that the condition should provide that covert medication could not be administered without a capacity assessment and best interests decision-making, that these assessments should be completed by the prescribing body, and that there should be a record of any covert medication administered.

DJ Clarke asked Ms Casely to confirm that she agreed there was no need to prolong the proceedings solely for this issue. Ms Casely agreed, saying, ‘Yes, any issues can be dealt with in the conditions and there are no live issues that require a decision from the Court’.

The Judge then turned to Ms Love, counsel for P through his ALR.

Ms Love raised concerns that the Local Authority had not considered the new AGNI test. One of the factors under the new approach is whether a person is consenting to their arrangements.

District Judge Clarke appeared confused by this submission, stating: “we know he is not consenting – that is why you are asking me to make a capacity and best interests decision about where he is”.

Ms Love explained that the Local Authority needed to speak to P and raised concerns that this had not yet happened in relation to his DoLS.

She accepted that the likelihood was that P was deprived of his liberty, but did not want the proceedings to conclude unless the Court was satisfied that the AGNI test was met, as there was insufficient up-to-date evidence.

When asked which factors were not supported by sufficient evidence, Ms Love identified P’s wishes and feelings. Her concern was that the Local Authority did not know P’s current wishes and feelings.

District Judge Clarke responded that, even if P were consenting — although nobody believed that he was — his medication and its sedative effects appeared likely to mean that any consent would not be considered valid.

Ms Love then asked for a statement to be filed that if P is deprived of his liberty that there be a COP 9. She stated, ‘I do not believe the Court could make a mental capacity assessment and best interests decision without all the relevant factors being considered’.

The Judge questioned what exactly Ms Love was seeking, emphasising that a BID was different from a deprivation of liberty.

At this point, District Judge Clarke explained to P’s family what was being considered while giving Ms Love some time to formulate her position.

The Judge explained that there were now two potential outstanding issues.

The first concerned covert medication. P’s wife confirmed that covert medication was not currently being administered, although she said that if P refused his medication, she thought it would probably be best for him to receive it covertly.

District Judge Clarke explained that P’s wife might well be right that covert medication would be in his best interests, but she was not satisfied that it should be permitted without a mental capacity and best interests decision, with input from the prescribers.

She explained that, at the previous hearing, she had not been willing to conclude the proceedings. However, having reviewed the evidence, she was now aware that P was compliant with his medication and that covert medication was not being administered.

The second issue was whether P remained deprived of his liberty under the new AGNI test.

What does AGNI change?

The Judge explained that P had previously been considered deprived of his liberty under the Cheshire West test. Following AGNI, however, the Court must apply a multifactorial approach.

The factors include the length and type of restrictions and how ordinary or normal those restrictions are. Importantly, consideration must also be given to whether the person is consenting and whether they can give valid consent for the purposes of Article 5 ECHR (as opposed to the domestic definition of consent).

The Judge explained that medication regulating a person’s emotional responses could potentially affect their ability to raise or maintain an objection to their arrangements.

This made the question of consent particularly important in P’s case.

P’s wife told the Court that P was in the best place and that the family was happy for the proceedings to conclude. She stated that P “would be horrified if something like this was going on for him”.

The family nevertheless wanted something in place to address covert medication. It did not need to be ‘urgent’, but ‘something should be put in place as we may go through another phase where P rejects his medication’.

DJ Clarke thanked the family for their input and turned to Ms Love.

Ms Love continued to express concerns about what would happen if P stopped taking his medication.

When District Judge Clarke asked what she wanted the Court to decide, Ms Love stated that covert medication should not be administered without a mental capacity assessment and best interests decision.

The Judge then asked a more fundamental question: if that was the desired outcome, what would be achieved by keeping the proceedings open?

Ms Love explained that no capacity assessment had been undertaken specifically in relation to covert medication. She said that she was not comfortable with the issue being dealt with solely by a condition and requested a section 49 report.

On the AGNI issue, she asked the Local Authority to update its DoLS paperwork to reflect the new test.

The Judge repeatedly returned to the question of proportionality. Why should the proceedings continue beyond the hearing if the remaining issues could be addressed through directions or conditions?

Ultimately, District Judge Clarke was not persuaded by Ms Love’s submissions and concluded that there was little benefit in prolonging the proceedings.

Applying the AGNI test: Is P validly consenting?

The Judge then turned to the restrictions imposed on P.

He is subject to onerous restrictions. The doors are locked, he is almost always supervised and is checked on an hourly basis. His placement is intended to be permanent and these restrictions were implemented for his care and support.

The Relevant Persons Representative (RPR) reports showed that P does not consent to his care arrangements. He wants to return to his family home and was previously resistant to the care.

The Court also considered that P is administered psychotropic medication, namely lorazepam. This was another factor indicating that he is not validly consenting to his deprivation of liberty or to the arrangements themselves.

Looking at the factors as a whole, District Judge Clarke concluded that P was deprived of his liberty.

But that did not mean the proceedings themselves needed to continue.

When is it proportionate to keep a case open?

Having concluded that P was deprived of his liberty, the Judge considered whether there was any benefit in continuing the proceedings.

She identified the impact on P, including the possibility that he might continue to believe that returning home remained an option while the proceedings remained open. She also considered the costs and resources involved, as well as the impact on the Court and P’s family.

Taking all of these factors together, she was not persuaded that there was merit in leaving the proceedings open. The remaining issues could be dealt with outside the proceedings.

The Court therefore concluded the matter, while making clear that the position would need to be reconsidered when the standard authorisation was renewed.

The Local Authority would be expected to reconsider the AGNI factors on review. If P’s RPR or family brought to its attention that P had changed his opinion and was consenting to his arrangements, this would also need to be considered.

The Judge intended the order to record the Court’s decisions and the expectation that the Local Authority consider the AGNI factors when reviewing the standard authorisation.

Reflections

As an RPR advocate, I found this a particularly interesting hearing to observe. I was able to see how a section 21A challenge can develop beyond the initial objection and lead to scrutiny of the wider care arrangements. In this case, the issue of covert medication had emerged from the original challenge, demonstrating how these proceedings can prompt examination of aspects of P’s care that may not have been the initial focus of the appeal.

It was also the first time I had observed the application of the new AGNI test in a post-AGNI hearing. The question of whether P was validly consenting was particularly significant, and I was interested to see how the Court approached it in practice. In this case, I was reassured by the focus on the sedative effects of P’s medication when considering whether his apparent compliance could amount to valid consent. However, it also made me question how “valid consent” might be interpreted in cases where there is no obvious factor, such as the sedative effects of medication, which might explain a person’s apparent change in behaviour.

In my work as an RPR advocate, I have had clients who repeatedly object to their DoLS yet become compliant with personal care and medication. This can happen because complying makes daily life easier, or because a person becomes tired of physically resisting their care. Their behaviour may therefore change without their underlying wishes or feelings necessarily changing with it.

I question whether there is a risk that a change from resistance to compliance could too readily be interpreted as evidence of consent. If someone was previously considered to be deprived of their liberty but subsequently appears to consent to their arrangements, it seems important to consider not only whether their behaviour has changed, but why it has changed.

This is particularly significant because a finding that someone is not deprived of their liberty has consequences beyond the label itself. Individuals who are deprived of their liberty benefit from independent checks and safeguards which may not apply in the same way if they are considered to be consenting to their arrangements. There is therefore a potential risk that, if apparent compliance is treated too readily as valid consent, an individual could lose those safeguards without sufficient consideration of whether they have genuinely changed their mind, become resigned to their circumstances, or simply stopped resisting.

Aside from the substantive issues, I thought this was one of the most transparent hearings I have observed. Both for P’s family and for me as an observer, the Court took care to explain the different legal tests, provide context from previous hearings and give P’s family multiple opportunities to raise their concerns. It demonstrated to me the value of the collaborative nature of Court of Protection proceedings: by allowing the parties and P’s family to contribute throughout the hearing, the Court was able to scrutinise different aspects of P’s care and ensure that issues were not overlooked.

Maria Maier is an aspiring barrister with an interest in the Court of Protection. She is currently working as a Relevant Person’s Representative (RPR) and Rule 1.2 Representative for adults who lack mental capacity and are deprived of their liberty under the Mental Capacity Act (MCA).  She has previously blogged for the Project here: Court approves sedative PRN medication  and Five Practical Tips For Observing Your First Court of Protection Hearing  She will begin her Bar Course studies in September 2026. Her LinkedIn is here.

A remarkable turnaround: Updating the “vile judgment” case

By Amanda Hill, 13th August 2026

As I write this in August 2026, Caroline Grady[1] is the primary (unpaid) carer for her mother, now in her eighties, who continues to live in her own home. Caroline visits every day and works alongside paid carers, who attend four times daily, to ensure her mother receives the care she needs. She can visit whenever she wishes and has unrestricted, unsupervised contact with her mother.

This is a remarkable turnaround.

For two years, between October 2023 and October 2025, the court banned Caroline from any unsupervised contact with her mother, the protected party ‘P’, including speaking to her on the phone – all calls had to have the speakerphone on. Norfolk County Council had arranged a 24-hour live-in care package and carers monitored their meetings and conversations, including recording what they said to each other.

This blog outlines the “Background” to the case and then describes in more detail what happened in the two most recent hearings, on 22nd October 2025 and 23rd March 2026.[2]

Background

This case, COP 14187074, is one the Open Justice Court of Protection Project has been following for a long time and we have published a number of blogs (see Appendix).[3]

In early 2023, Caroline’s mother, then in her late 70s, was in hospital with a chest infection.  While she was there, hospital staff and a hospital social worker became concerned about the mother/daughter relationship. The hospital made a safeguarding referral to the local authority, Norfolk County Council.  Caroline’s mother was discharged home in early May 2023. A few months later, following an alleged lasagne-throwing incident in late September 2023, a care plan, including live-in 24 hour care, was put in place, beginning in October 2023. The incident also led to Caroline being arrested for actual bodily harm and forbidden from seeing her mother for 3 months. She was never charged by the police. At an initial Court of Protection hearing, DJ Russell made an order declaring that there was reason to believe Caroline’s mother lacked capacity to conduct proceedings, and at a hearing on 17th January 2024, HHJ Beckley concurred.

At the same hearing he asked Caroline to give a number of “undertakings” (for more information about these, see “Make a legal promise to a court“). These included a promise only to have contact with her mother with a carer present. She was also asked to undertake not to use threatening or intimidating words or behaviour with the carer or with her mother, and not to cause her mother “upset or distress”. Undertakings have a penal notice attached to them, which means if somebody breaches them, they can be sent to prison. The judge also asked Caroline to agree not to use the Lasting Powers of Attorney. This was in advance of a fact-finding hearing, applied for by the local authority, which would establish whether or not Caroline had exerted coercive control over her mother.

At the fact-finding hearing in October 2024, Mrs Justice Arbuthnot found that Caroline’s mother lacked capacity to conduct proceedings, to decide about care, and to manage her property and affairs, but she did have capacity to decide about contact. The judge also found, on the balance of probabilities, all the allegations against Caroline to be “proved” or “found”, and declared that Caroline had undue influence over her mother.  The court invoked the inherent jurisdiction to protect Caroline’s mother and maintained supervised contact only, this time by court order rather than an undertaking. An injunction with 11 terms was added to the Lasting Power of Attorney for Health and Welfare (§75 of the judgment):

The terms state that Caroline:

1) … shall not install any camera, listening equipment or loudspeaker in [P’s]’s property, whether live-feed only, or live-feed plus recording…..

2) … shall not tell or suggest to [P’s]carers how to meet [P’s] care needs, or purport to hire or dismiss carers

3)…. shall not lie to, threaten, harass or intimidate [P]

4) …  shall not force [P] to exercise. 

5) …. shall not force-feed [P]

6) …..shall not mention or threaten to send [P] to a care home, or to Switzerland. 

7).… shall not deny [P] access to healthcare assessments or interventions. 

8)…..shall not take steps to prevent [P] from being administered prescribed medication. 

9) … shall not seek to discharge [P] from hospital against medical advice. 

10)…. shall not take steps to prevent social services and other social care, or healthcare practitioners from visiting or speaking with [P] alone. 

11)…. shall not take steps to move [P] to another place of residence.

In January 2025, Caroline was found to have been in contempt of court for breaching the undertakings she had given the court in January 2024. She was found to have upset her mother three times. She was found to have had unsupervised contact with her mother by not putting the phone on speakerphone all the time. She was found to have used the words “care home” in front of her mother, and to have told her mother a lie. It was open to the judge to commit Caroline to prison for these breaches of undertakings, but instead she fined her £500.

Normally, the names of people who are at risk of being committed to prison are made public in the court lists and in published judgments (and in any reports about the case). In this case, however, the judge did not authorise publication of her name. A court observer (Celia Kitzinger) made an application to remove the ban on publishing Caroline’s name – and other information about her which included the familial relationship between Caroline and the protected party. This was so that Open Justice Court of Protection blogs already in the public domain could be linked to the published judgment. The application was successful.

Caroline wants to give her side of the story and she wants the court proceedings to be publicised.  She gave her reaction to what she calls the “Vile judgment” in the blog of September 2025 (see Appendix).

Caroline did not  – and does not – accept all the “facts” that the Court found in the fact-finding hearing of October 2024. (In the civil court the ‘balance of probabilities’ test is applied so the probability that the “fact” is as the court determined can be as low as 51%.) Those facts that Caroline does accept are matters she understands and interprets very differently from the Court’s framing of what happened.

Caroline sought greater freedom to see her mother without supervision shortly after the fact-finding hearing. In December 2024 she applied for unrestricted contact on Christmas Day. The family wanted twelve hours together but the local authority only wanted them to have two.  The court finally authorised six hours, provided Caroline’s partner was present throughout.

Since the April 2025 hearing that concerned the Transparency Order and reporting restrictions, there have been two more hearings to discuss substantive issues, Caroline’s mother’s care, contact and the injunction.

The hearings in October 2025 and March 2026 reflect how significantly the case has evolved. By October 2025, the local authority had concluded that 24-hour live-in care was no longer necessary and sought court approval to replace it with four daily care visits supported by assistive technology. The court agreed, bringing an end to all restrictions on contact between Caroline and her mother. In October 2024, as Caroline’s mother had been assessed as having capacity to make decisions about contact, the inherent jurisdiction was invoked, instead of the Court of Protection. This “dropped away”, to use the judge’s words, after the October 2025 hearing.

Less than ten months after the family had pleaded to spend some hours together, unsupervised, on Christmas Day 2024, the court had lifted all restrictions on contact.

The March 2026 hearing addressed whether all the terms of the injunction attached to Caroline’s Lasting Power of Attorney for Health and Welfare could now be removed. The court decided they should remain in force for a further six months, with a final hearing listed for October 2026 to determine whether they should continue and to bring the proceedings to an end.

I will now set out in more detail what happened during the October 2025 and March 2026 hearings. The legal teams have remained largely unchanged throughout the proceedings I have observed. Mrs Justice Arbuthnot has presided over each hearing, Dr Oliver Lewis has represented Norfolk County Council, while Malcolm Chisholm has represented Caroline’s mother through the Official Solicitor[4].

The hearing of 22 October 2025

The October 2025 hearing concerned the authorisation of a significant change in Caroline’s mother’s care arrangements. Norfolk County Council had concluded that the 24-hour live-in care package was no longer necessary and sought the court’s approval to replace it with four daily care visits supported by assistive technology. If approved, the change would also bring an end to the supervision of contact between Caroline and her mother.

The remote hearing lasted just under two hours. Caroline joined from her mother’s home, together with her parents and her McKenzie friend, Arthur Stokes. During the hearing Caroline welcomed the fact that someone from the Open Justice Court of Protection Project was observing, commenting that “no family should be put through what we’ve been.”

The following paragraphs summarise the main content from the position statements.

The LA position

The local authority’s position was that the live-in care package had never been commissioned because of Caroline’s mother’s care needs alone. Rather, it had been introduced in October 2023 to protect her from the risk of abusive and controlling behaviour of her daughter. The authority argued that the protective purpose of the package had now been fulfilled. It noted that there had been no further incidents since the fact-finding of October 2024 and considered that Caroline had demonstrated an improved ability to regulate her behaviour.

The local authority also relied on Caroline’s mother’s own wishes. The position statement records her words:

“I am old now, I am in my 80s and I want a proper and normal life. I do not want to be somebody who is monitored and watched all the time. It is hurtful and I am not happy with that, who would be? It is not like they are a relative. They are always there and it is horrible”. (§15, LA PS)

If the 24-hour package of care was removed: “it would feel like heaven…….I just don’t feel as though I have got a life anymore at the moment. I feel like I am the guilty one, like I am being punished. At my age, I don’t think it is right”. (§18, LA PS).

Caroline’s mother was also quoted as saying that she was very happy to have unsupervised contact with her daughter.

To replace the live-in care package, the authority proposed four visits a day by paid carers together with assistive technology, including cameras without audio capability.

Caroline Grady’s position

Caroline took a different view. She argued that the live-in care should remain because she was concerned about her mother’s safety. Although she wanted unrestricted contact restored, she said she would rather accept continued supervision than see the 24-hour care package withdrawn. If live-in care did end, she argued that any replacement camera system should include audio so that she could speak to her mother in an emergency.

The Official Solicitor’s position

Representing Caroline’s mother through the Official Solicitor, counsel agreed that the 24-hour package could end, although he suggested a gradual transition. He emphasised that Caroline’s mother consistently wanted unrestricted contact with Caroline. But he submitted that the injunction terms attached to Caroline’s Lasting Power of Attorney should remain in place for the time being as an important safeguard.

As the option of 24 hour care was no longer being offered, the court could not order it to be continued, and did not suggest that it should be.  The judge observed that such packages are very unusual and that many older people rely on more limited support or fund additional care themselves. Caroline maintained that the decision was driven by financial considerations rather than her mother’s welfare, but the judge said there was no evidence of that.

Counsel for the Official Solicitor acknowledged the progress that had been made since the fact-finding hearing, remarking that the improvements were “to Miss Grady’s credit”.

Caroline questioned how the contact restrictions could be lifted while the injunction terms affecting her Lasting Power of Attorney remained. Counsel for the Official Solicitor explained that the two issues arose under different legal jurisdictions: decisions about contact had been dealt with under the court’s inherent jurisdiction, whereas the injunction terms regulating Caroline’s use of her powers as attorney remained matters for the Court of Protection.

The principal point of dispute concerned the proposed camera system. Caroline wanted audio capability so that she could reassure or guide her mother if she saw her fall. The local authority opposed this, arguing that an audio link could enable Caroline to resume “directing”, ie controlling her mother.  The local authority  insisted that any replacement system should provide video only. Caroline asked whether existing equipment could simply have its audio function disabled, but the authority required a new system to be installed. Caroline explained that she would have to pay for this new equipment, as all of her mother’s savings had been spent at the beginning of the court case (when she wanted to appoint her own legal representative.)

In giving judgment, Mrs Justice Arbuthnot concluded that the protective purpose of the supervision order had come to an end. She noted that there had been no repeat of the behaviour identified in the fact-finding judgment and that this was to Caroline’s credit. Most importantly, Caroline’s mother wanted both the live-in care package and the supervision of contact to end. As she had capacity to decide who she wished to see, the inherent jurisdiction order was discharged with immediate effect. Caroline and her mother were free to spend time together without restrictions, whenever they wanted.

The court also approved the replacement care package of four daily visits supported by assistive technology. The remaining issue—the future of the injunction terms attached to Caroline’s Lasting Power of Attorney—was deferred to the March 2026 hearing.

The hearing of 23 March 2026

This hearing addressed the issue of the remaining injunction terms, as well as reviewing Caroline’s mother’s wellbeing under the new arrangements.

By this stage, the arrangements approved in October 2025 had been in place for several months. Caroline’s mother remained at home, supported by carers visiting four times a day and assistive technology. Caroline continued to play a central role in her mother’s care and enjoyed unrestricted contact with her. The parties agreed that these arrangements were working well for Caroline’s mother. Counsel for the Local Authority started his submissions be saying that “She’s looking good and she says she’s feeling good.”

Counsel for the OS started his submissions by saying that it was a “pleasure to have [Caroline’s mum] back in court looking so well” and the judge concurred. He said that Caroline’s mother had told him she feels “8 out of 10”.

Unlike the previous hearing, this one took place in person, although I observed remotely. Caroline represented herself without her McKenzie friend, Arthur Stokes, who was unavailable. Her mother attended court, together with Caroline’s father and partner.

Counsel for the local authority maintained that there remained a significant risk of Caroline reverting to the behaviour identified in the October 2024 judgment. Particular emphasis was placed on the dispute over the camera system. Caroline had continued to argue that audio would enable her to reassure her mother in an emergency, but the local authority maintained that it would also allow her to direct her mother and interfere with the carers. It submitted that there was no care benefit to restoring audio and that Caroline’s mother herself did not want it.

At this point in the hearing, Mrs Justice Arbuthnot questioned whether all of the injunction terms remained necessary and explored whether a more limited approach might be appropriate. She said that one option was a “pick and mix” approach, so the first injunction (relating to installing “any camera, listening equipment or loudspeaker in [P’s]’s property, whether live-feed only, or live-feed plus recording”) could be left for “say 12 months”. She said she was conscious that there had been proceedings for “two to three years” – with the implication that it might be appropriate to bring proceedings to a conclusion rather than returning to court every six months.

Counsel for the Official Solicitor similarly acknowledged that the proceedings should not continue indefinitely. However, he argued that Caroline’s continuing wish to restore the audio system demonstrated why at least some protection remained necessary. He suggested that the first injunction term, preventing the installation of cameras with audio capability, might need to remain in force even if the others were eventually removed.

Caroline explained that her concern about audio arose from previous occasions when she had used the system to reassure her mother after falls. She said that she wanted only to be able to communicate with her mother in an emergency and described herself as her mother’s primary carer. She accepted that she could sometimes be overprotective but denied that her motivation was to control her mother.

Caroline and her father criticise the court

In her submissions to the court, Caroline returned to the findings made in October 2024. She reiterated that she continued to dispute aspects of the fact-finding judgment, including findings relating to force-feeding and other incidents. She accepted that she had to live with the court’s decision but maintained that some of the events had been misunderstood or mischaracterised. The judge responded that those findings had been made after hearing the evidence and would not be revisited.

Caroline’s father also addressed the court, in a statement Caroline read out for him. He expressed the family’s view that the proceedings had had a profound impact on their private family life and urging the court to bring the litigation to an end. He used the term “Totalitarian State” in his statement.

After hearing Caroline’s and her father’s statements, the judge seemed to have changed her mind. She indicated that, rather than just keeping the first injunction term about audio on the camera, as she had suggested earlier in the hearing, she was now minded to keep them all.  She remained concerned about the risk of Caroline reverting to the behaviour identified in the fact-finding judgment. While acknowledging the progress that had been made and recognising Caroline’s commitment to her mother, she considered it significant that Caroline continued to reject important findings made by the court and remained determined to restore the audio system despite her mother’s wishes.

Following a short adjournment, the parties discussed whether the injunction terms might instead be replaced by undertakings from Caroline. This would have required her to give what the judge called “just promises to the court” not to do what the injunction terms currently forbade her from doing.

Caroline declined to give “undertakings”. She said she found them “scary”. Although she would have preferred the injunction terms to be removed altogether, she said she would rather they remained than give “undertakings”. I don’t find this reaction surprising, given that she could have gone to prison in January 2025 for breaching previous undertakings. Undertakings are also generally in force “until further order of the court” – so forever, unless they are discharged by the court at some point in the future

Mrs Justice Arbuthnot ultimately concluded that the injunction terms should continue for a further six months. She accepted that Caroline’s mother was now living successfully under the revised care arrangements. She also recognised Caroline’s obvious love for her mother and the improvements that had taken place since the fact-finding hearing. Nevertheless, she remained satisfied that the injunction continued to provide appropriate protection while the parties adjusted to the new arrangements.

The court did, however, remove the term preventing Caroline from moving her mother to another residence (11), leaving the remaining ten terms in force. It also clarified that the order did not prevent Caroline from discussing her mother’s day-to-day care with carers where they invited her views, addressing concerns that ordinary communication might place her in breach of the injunction.

The judge made clear again that she wished these proceedings to end. A final hearing was listed for 8 October 2026 to determine whether the remaining terms of the injunction should continue and, if possible, to conclude the litigation. I plan to observe this hearing.

Amanda Hill is a PhD student at the School of Journalism, Media and Culture at Cardiff University. Her research focuses on the Court of Protection, exploring family experiences, media representations and social media activism. She is a core team member of OJCOP. She is also a daughter of a P in a Court of Protection case and has been a Litigant in Person. She is mainly on LinkedIn (here), but also sometimes on X (@AmandaAPHill).

Appendix

In chronological order, starting with the most recent down to the earliest:


[1] Caroline Grady can be named after Celia Kitzinger made a successful application to the court for reporting restrictions to be varied. There is a  published judgment about the application (Norfolk County Council v CA & Ors [2025] EWCOP 16 (T3) in April 2025)

[2] In addition to observing the hearings, I have corresponded with Caroline and interviewed both her and her McKenzie friend, Arthur Stokes, as part of my PhD research, and I draw on this research in writing this blog. I also received the parties’ position statements for both hearings which helped my understanding of the issues before the court, and which I use for writing this blog. I have also drawn on the published judgments.

[3] We’ve published five blogs about it since March 2024 (as listed in the Appendix), the most recent in September 2025 when we reported Caroline’s response to what she called the “vile judgment” (Norfolk County Council v CA & Ors [2024] EWCOP 64 (T3)).

[4] Except for the January 2025 committal hearing

Unlawful deprivation of liberty and the retrospective effect of AGNI: When the capacity requirement is not met

 By Celia Kitzinger, 9th August 2026
 
The standard authorisation of deprivation of liberty under the Mental Capacity Act 2005 has six qualifying assessments. The most significant of the six for the case I describe here is that the detained person must lack capacity to make their own decision about residence and care[1].  For adults with capacity to decide for themselves, a decision to deprive them of liberty cannot be made under the Mental Capacity Act 2005, and the Court of Protection has no jurisdiction. 
 
There are relatively few published judgments from cases in which P has been found to have capacity to decide on residence and care notwithstanding the existence of a standard authorisation saying that they lack that capacity[2].  Although we’ve reported  on several hearings in which protected parties have made that argument, judges have almost always determined, contrary to P’s views, that they lack the relevant capacity[3]. 
 
The case I’m reporting on here is one of the very few contested hearings I’ve watched in which P is found to have capacity to make her own decision, and the standard authorisation is therefore discharged. 
 
This case is also distinguished from others I’ve observed because it follows the Supreme Court decision in A Reference by the Attorney General for Northern Ireland [2026] UKSC 16 (henceforth AGNI). This landmark UK Supreme Court ruling fundamentally changed the legal definition of a deprivation of liberty. It explicitly overturns the long-standing Cheshire West “acid test” in favour of a flexible, multi-factorial assessment, with the effect that far fewer people are now considered to be deprived of their liberty. Since, in accordance with the orthodox declaratory theory of common law, Supreme Court decisions apply retrospectively (declaring what the law is now and always has been), it’s also quite possible that the conditions of a patient’s confinement and care may never, properly considered, have amounted to “deprivation of liberty” despite many years of standard authorisations.
 
So, in this case – COP 20018413 before DJ Glassbrook on 1st July 2026 – the s.21a challenge to P’s deprivation of liberty on the basis that she had capacity to make her own decisions could, in principle, have had as one of its outcomes a finding that she was not deprived of liberty and never had been.  For this P, who was considering whether to make an application for damages for a breach of her rights, this would have meant no Article 5 claim and no damages (even though the finding that she has capacity had been upheld).
 
Three key questions were addressed in the hearing.  The questions, and the recitals, declarations and orders relating to them in the approved order (issued 20th July 2026) are reported below. I’ll then report specifically on the hearing itself.
 
Question 1:  Is there sufficient evidence to rebut the presumption that P has capacity to make decisions about her residence and care such that the standard authorisation that currently applies should be discharged?
 
The judge found that P has capacity to make her own decisions about care and residence:  “IT IS DETERMINED on a final basis pursuant to s.15 MCA 2005 that: [P] has capacity to: (a) conduct these proceedings; (b) make decisions about her property and financial affairs; (c) make decisions about her residence; (d) make decisions about her care and support’….” (§1).  This means that “the mental capacity requirement in paragraph 15 of Schedule A1 MCA 2005 is not met…” (§2).  Consequently, the judge ordered that “the standard authorisation which came into force on 18 November 2025, and which was due to expire on 17th November 2026 is hereby terminated” (§3).
 
Question 2: If P has the requisite capacity now, from what date can it be said that she retained or regained that capacity?
 
The order records this: “The court makes no finding as to the date upon which [P] first had, or regained, such capacity […] save that it was no later than the date of [the independent expert consultant psychiatrist’s] assessment which formed the basis of the report of 21.1.26”.
 
Question 3: Do the circumstances of her residence and care amount to a deprivation of liberty under Article 5 of the European Convention on Human Rights as this is understood following AGNI  – and if so, was that deprivation of liberty unlawful?
 
Despite the change brought about by AGNI in the legal application of Article 5, the question of whether or not the conditions of P’s placement and care – now or in the past – were such as to amount to a deprivation of liberty (as a matter of law, now correctly understood) is not explicitly addressed in the final order.  Here’s how it reads:
 
4. The standard authorisation under Schedule A1 to the Mental Capacity Act 2005 authorising [P’]s deprivation of liberty ceased to satisfy the qualifying requirements once [P] had capacity to make decisions concerning her residence and care.
 
5. Accordingly, from the date on which [P] had such capacity, the standard authorisation was invalid and the deprivation of liberty to which [P] was subject was unlawful.
 
I have some difficulties with this because the order seems to conflate: (a) a standard authorisation and ‘deprivation of liberty’; and  (b) a standard authorisation that doesn’t satisfy the qualifying requirements with a ‘deprivation of liberty’ that is unlawful. 
 
First, it cannot be unproblematically assumed that a standard authorisation issued before the AGNI judgment was handed down on 2nd July 2026 does in fact evidence  ‘deprivation of liberty’ under the meaning of Article 5 ECHR, as it must now be interpreted following AGNI. I have observed other s.21a hearings in which parties challenging P’s ‘deprivation of liberty’ were informed, following AGNI, that P is now understood not to be deprived of their liberty – despite a standard authorisation saying that they are – with the result that the standard authorisation has been terminated while the arrangements for their residence and care remained the same[4]. In these cases, termination of the standard authorisation was not because P had capacity to decide on their residence and care, nor because changes were made to reduce restrictions relating to their residence and care, but because the pre-existing arrangements for residence and care were no longer, as a matter of law, constitutive of a deprivation of P’s liberty.
 
So, in this case, although it is correct to say that the standard authorisation was made (back in November 2024) to authorise arrangements for P’s residence and care that constituted a deprivation of liberty under Cheshire West, those same arrangements may have ceased to be a deprivation of liberty (with retrospective effect) following handing down of the decision in AGNI on 2nd July 2026. On my reading, then, the second part of §5 in the order is not something that simply follows (as implied by the word “accordingly”) from §4 and the first part of §5, because the effect of AGNI is to require analysis of whether P was in fact, as a matter of law, deprived of her liberty, notwithstanding the existence of a standard authorisation.
 
In fact, in the course of the hearing, the judge did address the question of whether, in this case, what constituted a deprivation of liberty in the Cheshire West sense continued to constitute a deprivation of liberty following AGNI, and he concluded that it did, drawing heavily (as have other judgments) on the presence of objection.  I was surprised that this did not make it into the order.
 
Second, the question of the lawfulness of a past deprivation of liberty does not follow automatically from a finding of P’s capacity. Restrictions on protected parties are very commonly in place where there is ‘reason to believe’ (s.48 MCA 2005) that they lack capacity in relation to any of the decisions needing to be made.  Once capacity is determined, a P found to have the requisite capacity is free to make their own decision going forward, but it is not usually suggested that the protection afforded P up to that point has been “unlawful”.  The court in this case had relied on s.48 MCA 2005 for its jurisdiction (as recorded in Recital G of the order), which would justify continued deprivation of liberty pending a final determination of capacity – at least insofar as the timescale complies with the Article 5(4) requirement for the lawfulness of a detention to be “decided speedily by a court”. There is a problem, as I see it, in that P’s application was made on 27th June 2025 and not decided until more than a year later on 1st July 2026, which may well not qualify as a “speedy” decision (though I have seen many other s.21a proceedings of similar duration). Based on what I’ve learnt about this case, it could reasonably be argued that there were good reasons for the court’s delay in reaching a decision – notably the problems with the first independent expert report (by a psychiatrist), and that expert’s recommendation to commission a second expert report from a different professional (an occupational therapist).  I find it difficult to square the judge’s declaration that P was unlawfully deprived of her liberty from a date “no later than the date of [the independent expert consultant psychiatrist’s] assessment which formed the basis of the report of 21.1.26”, with the fact that he had ongoing judicial oversight of the case at that point and did not discharge the standard authorisation, as was within his power to do, in January. So, I’m not sure I understand how the “deprivation of liberty” suffered by P between 21st January 2026 and 1st June 2026 could have been “unlawful”. I hope legally qualified readers of this blog might offer me some help with understanding this (please use the ‘Reply’ button at the bottom of the blog post).
 
One value in observing hearings, rather than relying on orders and judgments to understand judicial decision-making, is the insight they offer into how judges consider the evidence and balance opposing arguments in practice on the ground.  Some of the matters that puzzle me in the order were addressed in the course of the hearing.  I’ll first give some “Background” and then describe “The Hearing” (which included an oral judgment), and end with some “Reflections”.

1. Background to the hearing

Ms Smith (not her real name) is a woman in her fifties with a history of strokes and an acquired brain injury (I think from about five years ago). She has some cognitive impairment, including executive functioning difficulties, and some significant physical and mental health challenges, including mobility challenges that put her at risk of falls.  She lives in a 24-hour supported placement which she experiences as “restrictive, isolating and unsuitable for her needs”.  She describes life in the care home as “like prison” and feels she’s “lost years of her life to institutional care”[5]. 
 
In June 2025, Ms Smith made a s.21a application (through her litigation friend, the Official Solicitor) to challenge the standard authorisation that, on the face of it, makes it lawful to deprive her of her liberty.[6]  It was still the subject of ongoing proceedings, more than a year later.
 
The s21a challenge is based on Ms Smith’s claim that she has capacity to make her own decisions about where to live and receive care.  She also seeks a declaration that she’s been unlawfully deprived of her liberty since the beginning of her detention at the current placement: such a declaration would make possible a potential claim for false imprisonment and/or damages under the Human Rights Act 1998.
 
In December 2025 (I don’t know why not earlier), the court instructed a consultant psychiatrist to make an independent capacity assessment[7].  He  filed his report in January 2026. His findings are equivocal.  He found “strong evidence” she has capacity in relation to litigation, and said she “likely” has capacity to make decisions about property and affairs; it’s “plausible” that she has capacity for decisions about  care and support and it’s “finely balanced” as to whether she has capacity or not in relation to accommodation. This equivocation and lack of clarity led to uncertainty and dispute between the parties about the capacity evidence. Further questions were asked of the expert, who submitted an Addendum Report on 4th March 2026.  According to the judge, this “included a lot more words but didn’t actually help us with a lot more clarity, and Dr Z said it wasn’t possible to reach a definitive conclusion without an assessment by an occupational therapist”.  As recommended by Dr Z, on 13th March 2026, the judge directed a second independent expert report, this time from an occupational therapist. This second independent report was received in early June 2026, and was before the court at this hearing. 
 
The occupational therapist’s expert report concludes unambiguously that Ms Smith has the mental capacity to make decisions in relation to residence, care and support, medication management and alcohol use.  It also concludes that her current care home is not in her best interests as it’s “overly restrictive and does not sufficiently promote [Ms Smith’s] autonomy or rehabilitation potential”. The home environment, it says, contributes to “occupational deprivation, emotional distress, and social isolation” and that “while [Ms Smith] has ongoing vulnerabilities and a risk of falls, these factors do not justify the current level of supervision and containment when less restrictive alternatives may meet her needs”.  The report recommends a “less restrictive, rehabilitation-focused” placement with “a strengths-based approach focused on enablement rather than continuous supervision” involving “positive risk-taking principles balancing safety with [Ms Smith’s] dignity and autonomy”. 

The Official Solicitor accepts the expert report from the occupational therapist – and endorses, in particular, her finding that Ms Smith has capacity to make her own decisions about where to live and receive care.  The local authority does not accept that report and has raised various questions. For example, concerning the finding that Ms Smith has “at times minimised her support needs” they want to know “how that minimisation was taken into account” in determining her capacity. The local authority says that Ms Smith’s capacity remains in dispute and cannot be properly determined on the current written evidence alone, and that another hearing is needed, preferably in person with both experts in court,  to test the capacity findings.

2. The hearing

The hearing opened with the judge’s summary of and reflection on the case.  It was an “uncomfortable” situation, said DJ Glassbrook.  There was “significant evidence” before him, in the form of two independent expert reports, that the protected party either “plausibly” has or definitely has capacity to make her own decisions about where she lives and the care she receives, and “if she does, that means the court’s jurisdiction falls away”.  He’s a judge who routinely makes visible his “working out” of the case during the course of hearings, and he did so here.[8]
 
“The whole regime is geared towards one having the right to challenge a deprivation of liberty urgently.  Here we are, however, many months after the start, when capacity has been an issue for some time, and we had, can I say, a maybe unfortunate report from the psychiatrist earlier this year which was (pause) not as clear as many psychiatric reports might have been, and came up with the conclusions that there is strong evidence that this lady has capacity to litigate – I’ll come back to that – and also property and affairs, but that it’s finely balanced and “plausible”, the word used, either way concerning residence and support. So, questions were asked and then in March, Dr Z again said in the circumstances of this case we need the assistance of an occupational therapist – which is unusual, but there we go.  We have our Occupational Therapy report from 7th June and our OT concludes regarding the relevant areas that this lady does have capacity. Albeit she acknowledges that the challenges she’s had in life – possibly the brain injury included – influence aspects of her function and needs, but notwithstanding that, she concludes that she has capacity. And I have the Official Solicitor in support of that saying “Yes, she’s got capacity – make the declarations”.  And on the other hand, I have the Local Authority saying to me “we need more evidence”, and just over a page of questions – and saying not only that we need those questions answering, but we need an oral hearing.  Hmm…. That’s not an easy one.  First of all, if we’re going to have oral evidence, what do you need the written questions for? You can ask them in cross-examination – that may speed things up.  Then I’m thinking to myself, suppose the court and HMCTS can all accommodate a hearing, how long is it going to take to line up a hearing with the occupational therapist and the psychiatrist available?  And in the meantime, if I accede to the local authority’s wishes, the standard authorisation and hence the deprivation of liberty – somebody being locked up against her will – continues.  I use that emotive language[9] deliberately because this lady quite obviously isn’t happy where she is. If I go to the OT report, p. 661, “the current placement puts greater emphasis on containment than on rehabilitation and independence”, and p. 662 it’s “overly restrictive”. That’s not good to read. So, this isn’t a neutral observation – “Yes, there’s a lady locked up but she’ll be alright; let’s take our time”.  Far from it. This is a lady who there’s a distinct probability that her deprivation of liberty, right now, at twenty past two on 1st July,  should not be – and the Official Solicitor’s case is that there should be declarations to that effect by the end of today.  The Local Authority’s case is for a contested hearing – their preference is for contested evidence live in a courtroom, and we do that in two months, three months. There’s some really fundamental stuff to grapple with here.” 
 
Finally, the judge referred to case law from “the Blue Book”, citing two cases:

  • AJ v a Local Authority [2015] EWCOP 5 (heard by Baker J) “There is a positive obligation on the state to protect the liberty of those within its jurisdiction” and “there is an obligation on the State to ensure that a person deprived of liberty is not only entitled but enabled to have the lawfulness of his detention reviewed speedily by a court”.  The burden of protecting Article 5 rights is one, said the judge “for which ultimate responsibility lay with the local authority”. 
  • DL v LB Enfield 2019 (heard by HHJ Hilder) The judge read out the whole of §39 and part of §40
    “However large the numbers of a local authority caseload of persons being provided with care in the circumstances of their liberty being deprived it is imperative that those responsible for such conditions are never allowed to become cavalier about the significance of deprivation of liberty to the individual concerned and to society as a whole. In my judgment Article 5 rights do not become less precious because of the administrative burden of cases reliant on them. (§39)
    […] Article 5.4 is first and foremost a guarantee of a fair procedure for reviewing the lawfulness of detention. An applicant is not required as a precondition to enjoying that protection to show that on the facts of his case he stands any particular chance of success in obtaining his release. (§40)

These cases (and the extracts selected from them) refer to the duty of the public bodies to make the relevant applications to court – as this local authority had done. I don’t know whether the implication was that they had unreasonably delayed doing so: no such case was made at this hearing

Oral submissions from the local authority

The local authority was represented by Janice Wills (instructed by solicitors in Oxfordshire County Council legal services). Following the opening summary from the judge, Counsel began her submissions by saying:

“I have heard what you’ve said. The local authority sees it as imperative that this matter is determined and determined quickly.  My client had hoped that the report of [the Occupational Therapist] would bottom out the unhelpful recommendations of [the psychiatrist]. There are elements of the OT report we have problems with. We are not trying to be unhelpful.  The local authority social work team have read the report very carefully and there are some sweeping generalisations that are not evidence-based, and some areas that cause concern”.

She went on to detail some of these with reference to page and paragraph numbers in the document I did not have and said that the report was “going beyond its remit” (I’m not sure how – maybe in respect to the ‘best interests’ concerns?).  She ended with this: “The local authority is not saying that P does not have capacity. We are saying that the information we have been given does not evidence the conclusions reached.  We hope that the questions asked [the list of questions to which the judge had earlier referred], and asked very swiftly on receiving of the report – will go a long way to confirming that P does have capacity and we can move on”. (It seemed that the list of questions had already been sent to the OT.)

The judge then returned to the matter of Ms Smith’s litigation capacity. Both expert reports stated that she had litigation capacity and both the LA and the OS (the latter shortly to be discharged as a consequence) accepted that she had litigation capacity. He asked how it could possibly be the case that she had capacity to conduct the present legal proceedings (about her care and residence) if in fact – as the LA was concerned might be the case –  she was unable to understand, retain and weigh information about her care and residence. It was illogical, said the judge, for the LA to claim that she had litigation but not subject matter capacity, and there was case law to say so. This led to a protracted search for the relevant case law, which turned out to be a case decided by Mostyn J and from which the judge read the following paragraph: “I would go further and say that it is virtually impossible to conceive of circumstances where someone lacks capacity to make a decision about medical treatment, but yet has capacity to make decisions about the manifold steps or stances needed to be addressed in litigation about that very same subject matter. It seems to me to be completely illogical to say that someone is incapable of making a decision about medical treatment, but is capable of making a decision about what to submit to a judge who is making that very determination.” (§33, Re P [2021] EWCOP 27).
 
“There it is!” said the judge.  “Virtually impossible” and “illogical” – and if I substitute the care and residence decision for the medical decision, it seems to me that I have the identical position.  It is virtually impossible to conceive of circumstances where someone lacks capacity to make a decision about their care and residence, but yet has capacity to make decisions about the manifold steps or stances needed to be addressed in litigation about that very same subject matter”.
 
Counsel for the LA replied: “I hear what you are saying. You have heard the Local Authority’s position. The Local Authority remains concerned about capacity. I don’t know if I can help you further”.

Oral submissions from the Official Solicitor

Ms Smith, the applicant, was represented through her litigation friend the Official Solicitor by Laura Shepherd (instructed by solicitors at HAB law).  She asserted that Ms Smith has capacity to make decisions on residence and care.   An exchange with the judge ensued:
Judge:  And if this lady has capacity, it follows that the mental capacity requirement is no longer met, and from that it follows that the whole of the standard authorisation falls, doesn’t it?
LA: Yes, Judge.  We would add a declaration that since she has been detained she has had capacity and therefore she has been deprived of her rights.
Judge: I’ll come back to that. The fundamental point is that she has capacity, the mental capacity requirement is not met, therefore the standard authorisation is rescinded or discharged, and the consequence of that surely is that if this lady, when she is told that, says “it’s a nice sunny day, I’m going out”, she is free to go, whether she goes for a quick walk outside or leaves permanently.
LA: That’s right, Judge.
Judge: What would you say to the Mostyn quote?
LA: It is rare to have litigation capacity and not subject matter capacity.
Judge: Virtually impossible?
LA Yes, Judge.
Judge: In circumstances where I have to decide on the balance of probability… I appreciate that the case has been heard under s.48, “reason to believe”, but that has to have some sensible threshold, and if I were to suggest that “virtually impossible” implies that there is still some miniscule possibility, to my mind that doesn’t meet the sensible threshold of “reason to believe”.  I suspect you’d agree with that?
LA: Yes, Judge. The court should make its own decisions on each of the domains separately.
Judge: Agreed.  But there is an agreed position between the parties that we have a lady with litigation capacity. That’s a huge thing. We have no party telling me that she lacks capacity. Ultimately the court has to decide for itself – but it’s a huge thing if the parties are agreeing on it.  So I need to deal with that first. 
 
The judge turned next to counsel for the LA in case there was anything she wanted to say before delivering his oral judgment. She wanted to “make clear that the local authority is not being obstructive in any way, shape, or form. We just want the best outcome. We highlight again that significant concerns remain in the mind of the social work team”.

Oral decision on capacity

The judge reviewed the case law already discussed, including the relationship between litigation capacity and subject matter capacity: he read out the extract from Mostyn’s judgment (again) from “the standard textbook, page 2564 of Court of Protection Practice for this year” which he said “makes total sense”. His decision was this:
 
“In my judgment, this lady has capacity for decisions about her accommodation and her care in that accommodation. It follows from that that the standard authorisation cannot stand.  She is no longer deprived of her liberty, and if that means that this afternoon she fancies leaving, temporarily or otherwise, then so be it. And if that’s an unwise decision, so be it. We are not here to stop people making unwise decisions.  Nonetheless, she still needs somewhere to live and I imagine that will be in the very same placement, though its ability to stop her leaving must now cease.”

Oral decision on deprivation of liberty following AGNI

Having delivered his oral judgment about capacity, the judge then turned to AGNI. “If it’s relevant to look at AGNI and one looks at a lady who fulfilled the acid test requirement and one who does object to where she is, and we have restrictions which mean a greater emphasis on supervision and containment, when AGNI says to the effect that if there’s an objection, that’s probably very good evidence of deprivation of liberty, that’s evidence that even under the new test, that lady has been deprived of her liberty.”
 
There followed some discussion about the difficulty of establishing the date from which the “unlawful detention” commenced. In the absence of retrospective capacity evidence, the judge settled on 21st January 2026 “when Dr Z gave opinion that there was strong evidence of litigation capacity and for reasons already set out that would also cover capacity to decide on care and residence”.
 
It’s a fairly cursory assessment of ‘deprivation of liberty’ following AGNI from the judge, but perhaps all he felt was needed, given that both the OS and the LA accepted that Ms Smith’s “deprivation of liberty” survived the AGNI test.
 
According to the Official Solicitor’s position statement:

“As to whether following [AGNI], [Ms Smith’s] arrangements for residence, care and support amount to a deprivation of liberty, it is submitted that they do. She describes the arrangements as being “like prison” due to the restrictions on her movements and constant supervision. She is also strongly objecting to the placement and is not consenting to it in anyway. Considering the multi-factorial test set out by the Supreme Court, it is submitted that [Ms Smith] is being deprived of her liberty.” (Official Solicitor)
 
The matter occupies five paragraphs of the Local Authority’s position statement:

38. The Local Authority submits that [Ms Smith] is currently deprived of her liberty for the purposes of Article 5 ECHR.

39. That conclusion is properly reached by applying the multifactorial approach endorsed by the Supreme Court in [AGNI]. The Court is required to consider the cumulative nature, degree and intensity of the measures in place, rather than applying a rigid or mechanistic test.

40. Whilst the Local Authority has sought to reduce restrictions where it has been safe to do so, [Ms Smith] remains subject to a significant package of care, supervision and support. She resides in a regulated care setting, receives ongoing support with personal care, medication management, daily living tasks, emotional regulation and risk management, and continues to require staff oversight in relation to community access and her wider care needs.

41. The Local Authority acknowledges that some restrictions have recently been reduced. In particular, [Ms Smith] is now permitted greater access to kitchen facilities for meal preparation and hot drinks, subject to appropriate safeguards, and is able to walk independently within the grounds of the placement.  These developments reflect the Local Authority’s commitment to promoting [Ms Smith’s] autonomy and maximising her independence wherever possible.

42. However, when viewed cumulatively and in the context of [Ms Smith’s] overall care arrangements, the Local Authority considers that the degree of supervision, support and control that remains necessary amounts to a deprivation of liberty.  Relevant factors include [Ms Smith’s] continued need for a highly supported environment, ongoing supervision and monitoring, restrictions designed to manage identified risks, the absence of a viable less restrictive placement option at present, and the professional view that any move to a community setting would require a comprehensive package of 24-hour support broadly equivalent to her current arrangements.
 
I reflect (briefly) on these submissions in my closing section.

Ms Smith in person

Finally, counsel for the Official Solicitor asked whether Ms Smith could address the court herself. Ms Smith had been present throughout the hearing (although not introduced at the start) and I had noticed her listening intently. She was articulate and unsurprisingly emotionaI, apparently overcome with relief at the outcome of the hearing.

Ms S: I just want to say that I think it’s really important people aren’t considering that I had a very severe stroke and bleed on the brain. I couldn’t talk properly at the time and I couldn’t express what I was feeling. I was taken as an idiot. The first eight months I was here it was necessary, but after that, the next three and a half years I’ve been detained unlawfully.
Judge: I can understand that. This shows the importance of looking carefully at whether people- Even if the local authority has lots of cases on – not to lose sight of individuals. That’s what these cases are all about. Every now and again a s.21a case makes a huge difference to the individual, and yours is one of those.
OS: Ms Smith isn’t intending to leave the placement right away. She will work with staff to find somewhere to live. They still have Care Act responsibilities for her.
Ms S: I would like to be able to leave just to go into town and come back again. It’s not in my interests to move out right away. I have capacity and need to use it to find somewhere to live. I haven’t got anywhere to go. The staff here are nice. We have a laugh and a joke and it’s quite fun sometimes. (Tearfully)Thank you.

I offered Ms Smith (through her legal team) the opportunity to provide additional input into this blog post, but they did not receive a response from her about my invitation.

3. Reflections

It seemed clear to me that everyone in court wanted the best outcome for Ms Smith and in that sense the Court of Protection was working as it should.  But there was a strong difference of opinion as to Ms Smith’s capacity to make her own decisions and the risks of her living in a less protected environment.  The Official Solicitor promoted her autonomy (even at the risk of unwise decision-making). The local authority wanted to keep her safe. It’s a very familiar dilemma.

It would have helped the court to have had better evidence of her capacity available much sooner. it was now more than a year since the s.21a application, with capacity still contested, so the judge was in an unenviable position. It seemed to me that the uncontested evidence on litigation capacity was being used – in conjunction with Mostyn’s judgment – to do a lot of heavy lifting in the hearing in the judicial reasoning about Ms Smith’s capacity in relation to care and residence (and this was not necessarily reflected in the order).

This difficult situation was complicated by the changed definition of ‘deprivation of liberty’ since AGNI – and although it was addressed, it was not the focus of the court’s concern (for obvious reasons).
From the perspective of a court observer, seeking to understand how decisions about ‘deprivation of liberty’ are made following AGNI, the position statements and the judgment are disappointingly short on detail.  The local authority statement in particular seems to place great emphasis on the role of supervision, monitoring, safeguards and 24-hour support as constituting ‘deprivation of liberty’ – whereas my reading of AGNI is that even extensive supervision etc may fail to qualify as ‘deprivation of liberty’ under certain circumstances – as in the case decided by HHJ Burrows concerning a young woman subject to constant supervision and control including CCTV cameras[10]. The AGNI multi-factorial test would consider the purpose and proportionality of the extensive supervision and whether it is ‘normal’ for persons with that kind of disability.  I wonder whether the decison-making in this case reflects what Alex Ruck Keene, in his analysis of the (so far) only published DOLS judgment following AGNI, has called “the gravitational pull of Cheshire West”.[11] I note, additionally, that as in other cases I’ve observed, objection is treated as being highly relevant, post-AGNI, in constituting care arrangements as ‘deprivation of liberty’.[12] 

So, despite the judgment in this case, I will continue to wonder whether or not Ms Smith was still “deprived of liberty” following AGNI (on balance, I share the sense that yes she was), and also whether or not this can be said to have been “unlawful” since January 2026, and if so on what basis, given judicial oversight of the case during that period.

More broadly, I wonder whether a robust finding of “unlawful deprivation of liberty” made before 2nd June 2026 (when AGNI was handed down) could potentially fail today on the grounds that the circumstances of P’s detention never really constituted a “deprivation of liberty” properly considered. It’s probably academic in this particular case, but if at the time of the detention, everyone (the Official Solicitor, the supervisory body, the Court of Protection) proceeded on the basis that Article 5 was engaged, and a standard authorisation was obtained precisely because everyone accepted there was a deprivation of liberty, then surely a later reinterpretation of Article 5 should not retrospectively extinguish a potential remedy because the legal definition changed before the case was heard or before damages were assessed[13]. (Comments and feedback very welcome via the ‘Reply’ button.)

Finally, as all other cases concerned with deprivation of liberty and s.21a, I am grateful to the courts for ensuring that public bodies are (in HHJ Hilder’s words) “never allowed to become cavalier about the significance of deprivation of liberty to the individual concerned and to society as a whole” – a matter of particular and continuing importance since the Supreme Court decision in AGNI.

Celia Kitzinger is co-director of the Open Justice Court of Protection Project. She is on LinkedIn (here), and also on X (@KitzingerCelia) and Bluesky (@kitzingercelia.bsky.social)

Endnotes

[1] “Capacity” is as defined in domestic law – i.e. they must be able to understand, retain and weigh information relevant to the decision to be made. The other qualifying requirements are age (the person must be 18 or older), a diagnosed ‘mental disorder’, the arrangements are in their best interests, there’s no conflict with Mental Health Act detention, and the decision does not conflict with an advance decision to refuse treatment and is not opposed by someone holding Lasting Power of Attorney, or Deputyships etc.
[2] This judgment (made before the Supreme Court decision in Cheshire West) is interesting for determining both that P has capacity to make her own decisions about care and residence, and also that she is not deprived of her liberty despite not living at home as she wishes: CC v KK and STCC [2012] EWHC 2136 (COP)
[3] Influencing ‘best interests’ decisions: An eloquent incapacitious P For a case involving a P who successfully argued that she had litigation capacity see Strongly held beliefs do not equate to lack of litigation capacity: Judgment concerning Luba Macpherson’s appeal against committal to prison
[4] See these three blog posts in each of which a ‘P’ previously considered as a matter of law to have been deprived of their liberty now, post-AGNI, no longer meets the criteria: Considering ‘deprivation of liberty’ in a family home setting after AGNI; The irony and the AGNI: After years of traumatic DOLS experiences, P now no longer meets the criteria; What happens to restricted patients after AGNI? SJ Hilder considers the consequences 
[5] I’m grateful to the judge (and to the parties) for the uncontested decision to disclose position statements to me – enabling me better to understand the background to the case, the relevant facts the judge took into account and the basis upon which the judge arrived at his decision.  In writing this blog post I also draw on my contemporaneous notes from the hearing (as accurate as I can make them but unlikely to be completely verbatim) and the approved order issued on 20th July 2026.
[6] The initial application was to challenge the standard authorisation granted by the local authority that came into force on 7th November 2024.  The proceedings were subsequently reconstituted as a challenge to the standard authorisation dated 18th November 2025.
[7] Previous capacity assessments, completed by social workers (in relation to property and financial affairs, and in relation to residence and care) and by a senior carer (in relation to community access) between early June 2024 and early October 2025, found that Ms Smith lacked capacity in these areas of decision-making.  
[8] As I’ve commented before see: Objections (and breached conditions) after AGNI

[9] The judge commented later in the hearing on his use of “emotive language” when he said, “it sits with me that someone has been locked up – emotive language again – when it’s not been justified”.
[10] No published judgment but the blog post is here: Considering ‘deprivation of liberty’ in a family home setting after AGNI
[11] The judgment is Oxfordshire County Council v P [2026] EWCOP 33 (T2). The commentary is here: https://www.mentalcapacitylawandpolicy.org.uk/mental-capacity-end-of-term-report/
[12] In the absence of published judgments, I refer readers to two blog posts describing judicial decisions relying on ‘objection’ in formulating the person’s care arrangements as ‘deprivation of liberty’: Objections (and breached conditions) after AGNI (this is also DJ Glassbrook) and Judge authorises medical treatment and DOLS in hospital (Ms Powell KC was the judge). There are also cases where the absence of objection was cited as contributing to the formulation of the person’s care arrangements as not constitutive of a deprivation of liberty: What happens to restricted patients after AGNI? SJ Hilder considers the consequences; Considering ‘deprivation of liberty’ in a family home setting after AGNI (HHJ Burrows).
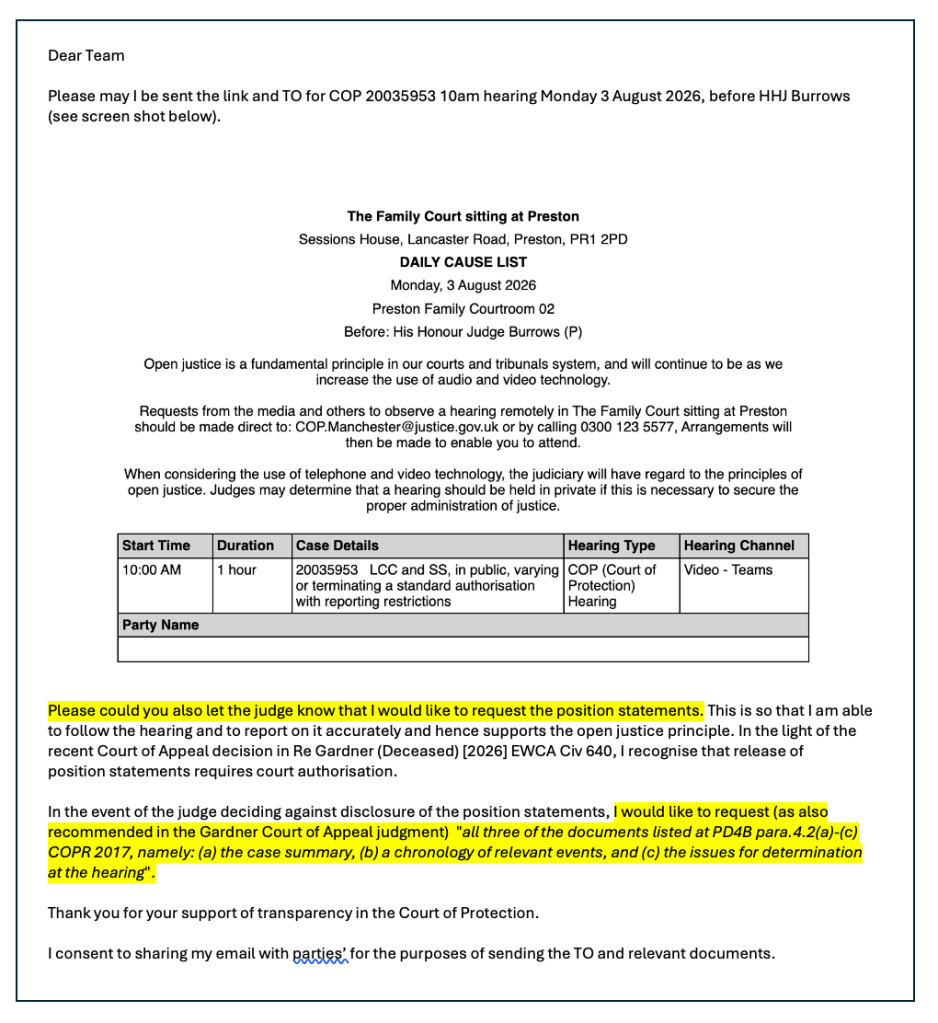
[13] The legal ramifications of In re Spectrum Plus Ltd are beyond my scope as a non-lawyer, but I’m told this judgment does raise the possibility, in “wholly exceptional” circumstances, of limits to the retrospective effect of judgments from the Supreme Court (or House of Lords as it was then) when the interests of justice demand it.

Fit to discharge or fit to section?

By Kim Dodd, 4th August 2026

The hearing I observed on the morning of Tuesday 28th July 2026 was the latest hearing in a long-running case (COP 13630253) that has been observed and blogged about several times before. At the last hearing in late June, as Elissa Novak explained in her blog (The ‘fit for discharge’ story continues: 10 months on), a plan was anticipated to be in place for P to leave hospital this week to return to her bungalow where she would be cared for by a team of (by then Makaton-trained) carers from the care provider team which has been supporting her in the hospital for the last week. This short blog aims to provide an update on the case in advance of the next scheduled hearing (planned for Friday 21st August at 9.30am, unless an emergency hearing is required in the meantime).

As a quick refresher, P is a woman with diagnoses of mild learning disability, emotionally unstable personality disorder, functional neurological disorder, dissociative disorder and elective mutism. She was admitted to hospital in April 2025 where she has been ever since, despite nobody advancing any argument that it was in her best interests to be in that setting.

The time and date of this hearing had been agreed at the last hearing (which I’d also observed) only a month earlier, so I was quite surprised when it didn’t appear on the listings on the Monday evening. I emailed the court early the next morning and was told: ‘Many thanks for your email. The list has now been amended with this hearing added. I have passed on your request to observe this hearing to Her Ladyship’s clerk who will be in touch’. After some chasing, I finally received the link at 9.24am for the hearing scheduled to start at 9.30am.

The hearing started at 9.38am, and lasted for seventy minutes. The lack of progress since the last hearing was clear, and Lieven J’s frustration was palpable. One of the main issues now is that P’s bungalow is not considered to be in an adequate state for her to return to. On top of this, questions have been raised (by the OS, represented again in court by Victoria Butler-Cole KC, and P’s siblings) about the suitability of the care provider.

It seems these questions have been driven by:

  • the carers’ failure to learn Makaton (despite this having been recognised as a fundamental aspect of suitable care for P)
  • the carers failing to acknowledge or to implement the advice on how to avoid triggering P that has been prepared by P’s siblings, and
  • a recent incident, on 20th July, of restraint (3 carers holding P down) which the OS and P’s siblings considered disproportionate. This incident was captured by the CCTV and had been circulated to all parties, though it transpired that neither the judge nor the OS had seen the footage. The applicant ICB and LA had seen the CCTV and read statements about the incident and reportedly felt, on balance, that the degree of restraint used was proportionate. Lieven J asked for the Order to reflect that all parties should watch the CCTV footage.

Whilst the potential MHA assessment which had been the subject of debate at the last hearing was not mentioned explicitly (and I therefore assume it didn’t happen), Lieven J noted that P being detained under the MHA remained a strong possibility given P’s increasing dysregulation in the hospital setting.

P’s siblings (who again spoke to the judge directly at times, despite being legally represented) were clear that, despite their ongoing desire for P to return to her bungalow, their ‘profound concerns’ were based on a decade of lived experience, which showed that P’s return home had broken down rapidly. They are adamant that the new care providers are ‘the worst agency they’ve been involved with’ and report receiving somewhere between 50 and 100 distress calls each day from P in which she begs them to prevent her having to go home with those carers. Their view is that if P returns home with this care provider, then her quality of life at home would be no better than it would be if she remained in hospital.

Lieven J expressed sympathy for their concerns but emphasised that P is not easy to deal with in her current state and that there had also been concerns about the previous care provider. In her typically pragmatic style, Lieven J also pointed out that the pool of carers the provider pulls from is ultimately one and the same, and that without that care provider there was no other available agency. Lieven J expressed concern that any change of plan with respect to the care-provider would inevitably lead to a six week delay at a minimum, during which time P would be ‘within millimeters of being detained under the MHA’.

To ensure some real progress is finally made, Lieven J proposed that she would chair a meeting next week with the key people involved (but without lawyers; ‘I love lawyers dearly, but they won’t help’). The purpose of the meeting would be for the OS and P’s siblings to talk to the care provider about how a care package can be put in place.

The next hearing in this case is scheduled for 9.30am on Friday 21st August, though Lieven J invited the OS to request an emergency hearing next week (first week of August 2026) should she (the OS) deem it necessary.

I hope to observe the next hearing and to be in a position to provide a further update on what is fast becoming (in my opinion) a case reminiscent of ‘Groundhog Day’, much to the detriment of P.

Kim Dodd has family experience as the daughter of a P in the Court of Protection and has previously blogged for the Open Justice Court of Protection Project. Having retired early from her own corporate career and studied for a Master’s of Law, Kim has developed her interest in law generally and particularly in the area of the law on coercive control. She is on LinkedIn (here).






